Showing posts with label survival rates. Show all posts

Wednesday, January 11, 2012

Cancer immunotherapy comes of Age,,Melanoma..Jim Breitfeller

Author:Ira Mellman1, George Coukos2 & Glenn Dranoff3

Nature:4 8 0 | NATURE | VOL 480 | 22/29 DECEMBER 2011

"Activating the immune system for therapeutic benefit in cancer has long been a goal in immunology and oncology. After decades of disappointment, the tide has finally changed due to the success of recent proof-of concept clinical trials. Most notable has been the ability of the anti-CTLA4 antibody, ipilimumab, to achieve a significant increase in survival for patients with metastatic melanoma, for which conventional therapies have failed. In the context of advances in the understanding of how tolerance, immunity and immunosuppression regulate antitumour immune responses together with the advent of targeted therapies, these successes suggest durable and long-lasting response in cancer patients."

We as patients of the Clinical trials are right in the middle of this awakening!!!!

Here is the article:

Cancer immunotherapy comes of age


“It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.”
~Charles Darwin~
Take Care,
Jimmy B

Photobucket

Tuesday, October 12, 2010

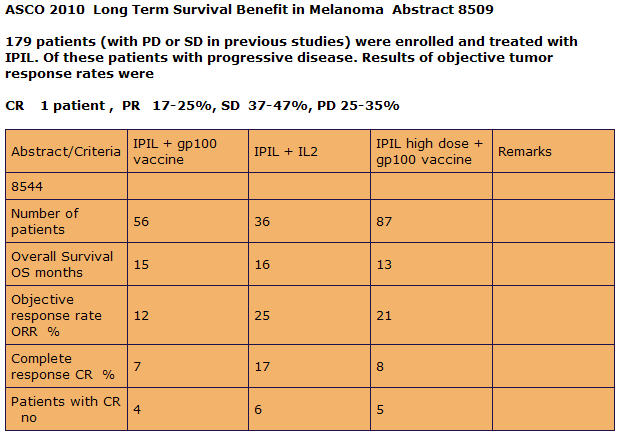
ASCO 2010 Long Term Survival Benefit in Melanoma...Jim Breitfeller


As you can see the combinatorial therapy of Anti-CTLA-4 and Interluekin-2 give the best complete response. I am convince that if they adjust the timing and dose, they will see an even higher response rate in overall survival.

The Making of an Immune Response by Combinatorial Therapy Using Anti-CTLA-4 Blockade and Interleukin-2

The paper that I am about to present to you is a culmination of research that was done base on my own experience as a stage IV Melanoma Patient. I wanted to know why my immune system responded and prove to myself and my doctors that it was not a statistical fluke. I dedicate this paper to all my fellow Melanoma Patients that lost their battle with the Beast, especially Bob Luker who fought so bravely but was unable to obtain Anti-CTLA-4 blockade due to the shortage proclaimed by Bristol Myer Squibb which halted compassionate drug use on 9-12-2008.

Most Melanoma tumors are accepted by the host’s immune system and progress even when they contain potentially antigenic proteins. This may be due to the tumor secreting immunosuppressive Cytokines like, TGF-Beta, IL-10, IL-4 and IL-6. TGF-β inhibits the proliferation and functional differentiation of T lymphocytes. TGF- Beta accelerates the expression of CTLA-4 by stimulated CD4+CD25– T cells. TGF- Beta requires CTLA-4 early after T Cell Activation to induce FoxP3 and generates adaptive CD4+CD25+ (Treg) Regulatory Cells. The tumor cells secrete TGF-Beta.

The Making of an Immune Response by Combinatorial Therapy Using Anti-CTLA-4 Blockade and Interleukin-2


“It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.”
~Charles Darwin~
Take Care,
Jimmy B

Photobucket

Saturday, July 31, 2010

In Stage IV melanoma patients, a high percentage of Tregs appears to be associated with shorter survival. Jim Breitfeller

In Stage IV melanoma patients, a high percentage of Tregs appears to be associated with shorter survival.

Received 12 February 2008 published online 03 June 2008.

Background

Melanoma often elicits a profound immune response, and this response has been exploited by various immune therapies. These immunotherapies ultimately fail, however, and advanced melanoma is uniformly fatal, suggesting the development of an immune escape mechanism. In this study, markers of immune escape including regulatory T cells (Tregs), dendritic cells (DCs), and TGF-β were evaluated in 14 Stage IV melanoma patients and correlated with survival.

Source:http://www.journalofsurgicalresearch.com/article/S0022-4804(08)00344-2/abstract

In Stage IV melanoma patients, a high percentage of Tregs appears to be associated with shorter survival


Just follow the Science!!!!!!


Results

Stage IV melanoma patients had a doubling of regulatory T cells compared to both normal subjects and stage I melanoma patients. There was a significantly higher number of DCs in all melanoma patients compared to normal subjects. Stage I melanoma patients had a significantly higher number of pDCs than normal subjects, and all melanoma patients had a higher concentration of mDCs than controls. Serum IL-4 and IL-10 were not detectable but serum TGF-β levels were significantly higher in stage I and stage IV melanoma patients compared to normal controls.

Conclusion

Advanced melanoma is associated with increased numbers of circulating dendritic cells and regulatory T cells. These data suggest that melanoma induces immunosuppressive DCs and regulatory T cells in the systemic circulation.


Source:http://www.springerlink.com/content/k0gk8740u3n75744/


“It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.”
~Charles Darwin~

Take Care,
Jimmy B

Photobucket

Thursday, June 10, 2010

Improved Survival with Ipilimumab in Patients with Metastatic Melanoma..Jim Breitfeller

Improved Survival with Ipilimumab in Patients with Metastatic Melanoma

Published at www.nejm.org June 5, 2010 (10.1056/NEJMoa1003466)

The New England Journal of Medicine


Improved Survival with Ipilimumab in Patients with Metastatic Melanoma


“It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.”

~Charles Darwin~

Take Care,

Jimmy B
Photobucket

Friday, December 25, 2009

CTLA 4 Success Rate melanoma trials.. Jim Breitfeller

The most interesting data was on ipiliumumab (abstract #9033), which looked at the effect of the agent on 18 and 24 month survival from 3 phase II trials dosed at 10mg/kg every 3 weeks (plus maintenance therapy Q12W from week 24 in appropriate patients) in advanced melanoma, where survival outcomes are usually poor. Ipilumumab is a fully humanised monoclonal antibody that targets T-lymphocyte antigen 4 (CTLA-4).

The 3 studies summarised were CA184-008, CA184-022, CA184-007.

The results clearly showed that:

- 12 month survival rates were >47%
- 18 month survival rates were >34%
- 24 month survival rates were >30%

"For previously treated patients, 24 month survival rates ranged from 24% to 33%.
Long term survivors included patients with progressive disease according to WHO criteria.
These results are promising but caution must be extended because a significant number of patients were lost to follow-up, which may reduce the reliability of the results. Ongoing biomarker studies are looking at predicting which patients are most likely to benefit from ipilumumab therapy.


Ipiliumumab


What did we learn from these trials? Well, there is an urgent need to define optimal endpoints for melanoma clinical trials in terms of response rate, PFS, OS and survival at 12 months. It is interesting that over the past 10 years the majority of abstracts have hyped the results in this disease as 'promising' or 'clinically active' regimens and yet very little in the way of new therapies have actually been approved by the FDA. Based on these data, I suspect it will still be a little while before we see some solid phase III data in malignant melanoma."


Take Care,

Jimmy B
Photobucket

Friday, September 25, 2009

MELANOMA: NEW THERAPY WITH IPILIMUMAB, VIDEO INTERVIEW PROF.A.EGGERMONT at ECCO September 2009

We are seeing the fruits of our Labor

Video interview with prof.Alexander Eggermont, Ecco Oncology President at 15 Ecco Esmo 34 European Oncology Congress in Berlin, september 2009.

You need to shut off my playlist to stop the music before you listen to the video.


Take Care,

Jimmy B
Photobucket

Bristol-Myers Squibb at Morgan Stanley Global Healthcare Conference 9/14/2009..Melanoma .Jim Breitfeller

Bristol-Myers Squibb at Morgan Stanley Global Healthcare Conference 9/14/2009

If you go to Bristol-Myers Squibb's website and click on investor, you will see:

Events and PresentationsBristol-Myers Squibb at Morgan Stanley Global Healthcare Conference
Monday, September 14, 2009
Webcast replay

If you sign up and play the webcast, you get the feeling that it all comes down to greed and money in my opinion. Market share, Patients, Doctors all in one breath.

Have patient become a comodity? We will vote with our feet and voices.

When they say, “What sets us apart? We believe it's our commitment to patients with serious diseases, our focus on finding innovative medicines that combat those diseases, and our dedication to extending and enhancing human life.”

All smoke and mirrors!!!!!!!

But if you listen and reach 25.55 minutes into the webcast, there is a question on Medarex and Ipilimumab. Fully human anti CTLA-4 monoclonal antibody in advanced clinical trials, Metastatic Melanoma. Phase III Data Overall Suvival data will be out shortly. With these results (I believe will be positive) in hand, I believe that Bristol-Myers Squibb (BMY) will apply for a biological licence from the FDA.

Biological products often represent the cutting edge of medical science and research. Also known as biologics, these products replicate natural substances such as enzymes, antibodies, or hormones in our bodies.

What is FDA's role regarding biological products?

FDA's regulatory authority for the approval of biologics resides in the Public Health Service Act (PHS). However, biologics are also subject to regulation under the Federal Food, Drug, and Cosmetic Act (FD&C Act) because most biological products also meet the definition of "drugs" cited within this Act.


BMY Webcast


Take Care,

Jimmy B
Photobucket

Thursday, July 23, 2009

Here is what Anti-CTLA-4 blockage can do!!!! Melanoma..Jim Breitfeller

Source:FORBES.COM

On The Cover/Top Stories

Targeting Melanoma

Robert Langreth 10.15.07, 12:00 AM ET

A new arsenal of therapies is aimed at a widespread and lethal skin cancer.


"Until recently researchers had little clue what molecular changes drive melanoma's rapid growth. But that has changed in a flurry of basic biology findings. "In terms of understanding what makes melanoma tick, in the past five years there has been an utter revolution," says Keith Flaherty, a physician at the University of Pennsylvania.

In 2002 gene researchers in the U.K. discovered that two-thirds of melanomas have a mutation in a growth-promoting gene inside skin cells called BRAF. The mutation causes the BRAF protein to become stuck in the "on" position, so it constantly sends a signal to the nucleus that it is time to proliferate. BRAF blockers are now in early-stage human trials at Novartis and separately at Roche, which works with partner Plexxikon. AstraZeneca is in midstage trials with 180 melanoma patients for a drug that hits a related target called mitogen-activated protein kinase kinase. "Every company I know of is interested in this," says Plexxikon Chief Executive Peter Hirth.

Therapies that trick the immune system into attacking melanoma are further along. Such immune system boosters have the potential to treat many types of cancer, but melanoma is one of the prime initial targets because it is one of the few cancers known to go into spontaneous remission on its own, indicating a possible immune response at work. The immune system activator interleukin-2 helps 15% of advanced melanoma cases and cures a few, but it produces such devastating side effects that patients must be hospitalized.

Pfizer's drug tremelimumab and Bristol-Myers Squibb's ipilimumab are antibodies to a protein called CTLA-4 (cytotoxic T-lymphocyte antigen-4) that acts as an emergency brake to prevent killer T cells from attacking healthy tissue. The antibodies bind to the CTLA-4, found on a cell's surface, and shut off the brake. Killer T cells then attack the cancer cells. Both drugs are in final-stage trials on hundreds of melanoma patients.

Much credit for the concept goes to immunologist James Allison, now at Sloan-Kettering. In the mid-1990s he theorized that CTLA-4 might prevent the immune system from mounting an effective response against tumors. Others were skeptical. But Allison showed in 1996 that he could shrink tumors in mice by injecting them with antibodies to CTLA-4.

Both Pfizer and Medarex, a biotech firm in Princeton, N.J., subsequently produced human antibodies to CTLA-4 and began testing them in patients a few years later. In 2005 Bristol-Myers Squibb paid Medarex $50 million in cash plus up to $480 in payments contingent on the success of Medarex's antibody.

At a meeting of cancer specialists last June Bristol-Myers and Medarex reported their drug shrank tumors in 46, or 13%, of 356 melanoma patients. The Pfizer antibody shrank melanomas in 7 of 84 patients in a midstage trial. The success rates were modest, but cancer doctors say that some patients may have had delayed responses. In some people tumors started to regress months after they had been declared treatment failures, says Bristol-Myers Vice President Renzo Canetta.

UCLA's Ribas calls the response rates "very low" and cautions that the anti-CTLA-4 drugs are just a first step. But even if the drugs improve survival only minimally, they are likely to be approved, he says. Bristol-Myers and Medarex are expected to finish key trials this fall. RBC Capital Markets analyst Jason Kantor pegged the odds of disappointing results "relatively high" in a recent report and rated Medarex an underperform; if the response rate is under 10%, it would make near-term approval "iffy", he says. Side effects of the drugs can include inflammation of the colon, thyroid or pancreas, or other autoimmune problems.

One reason for the limited response rate may be that some patients' T cells do a poor job of recognizing melanoma. To improve this situation, researchers are combining new antimelanoma vaccines with anti-CTLA-4 drugs. The idea is that the vaccines will train T cells to spot cancer, while the antibody will make sure the T cells remain activated long enough to do their dirty work.

Sharon Belvin was one of the first to try such a combination therapy. In May 2004, just a week before her wedding, she had developed a melanoma metastasis in her left lung. Belvin was only 22. The tumor grew through her chest cavity underneath her collarbone. Various chemo drugs and interleukin-2 produced nerve damage and other nasty side effects and didn't solve the problem. By June 2005 she had tumors in both lungs and could barely breathe or walk. Then Wolchok put her in a trial testing ipilimumab with an experimental Medarex vaccine. After only four treatments the tumors started to melt away. They were gone by mid-2006. The Jamesville, N.C. resident has been off therapy for a year and is pregnant with her first child, a girl due Feb. 10 2008."


By the Numbers

59,940 annual cases of melanoma in the U.S.

8,110 annual deaths.

99% five-year survival rate, localized disease.

15% five-year survival rate, widespread disease.

Source: American Cancer Society


Take Care,

Jimmy B
Photobucket

Sunday, May 31, 2009

Two-Year Survival Rate Ranging from 30 to 42 Percent in Metastatic Melanoma Patients Treated with Ipilimumab Melanoma..Jim Breitfeller

Results from Three Phase 2 Studies Reported a Two-Year Survival Rate Ranging from 30 to 42 Percent in Metastatic Melanoma Patients Treated with Ipilimumab (10 mg/kg)

PRINCETON, N.J.--(BUSINESS WIRE)--May. 31, 2009--Bristol-Myers
Squibb Company (NYSE: BMY) and Medarex,
Inc. (NASDAQ: MEDX) today announced updated survival results from
follow-up extensions of three Phase 2 ipilimumab studies of patients
with advanced metastatic melanoma (Stage III or IV). The two-year
survival rate ranged from 29.8 to 41.8 percent in patients who received
ipilimumab (10 mg/kg). Results of the survival data were presented at
the 45th Annual Meeting of the American Society of Clinical
Oncology in Orlando, FL., May 29 -- June 2, 2009.


The results are based on follow-up of up to 37.5 months (median
follow-up ranging from 10.1 to 16.3 months) of the patient population
from studies 008, 022 and 007 treated with 10 mg/kg of ipilimumab
(induction and maintenance) and, specifically, showed:


Two-year survival rate of 32.8 percent (95% CI: 25.37%- 40.49%) in
patients who had progressed while on or after receiving standard
treatment (Study 008, Abstract #9033);


Two-year survival rate of 29.8 percent (95% CI: 19.13%- 41.14%) in
patients who were previously treated, relapsed or failed to respond to
experimental treatment or were unable to tolerate currently approved
therapies (Study 022, Abstract #9033);


Two-year survival rate of 40.6 percent (95% CI: 27.12%- 54.37%) and
41.8 percent (95% CI: 28.30%- 55.46%) in patients receiving ipilimumab
plus budesonide or ipilimumab plus placebo, respectively, which
included treatment-naïve patients and patients previously treated with
therapy other than ipilimumab (Study 007, Abstract #9033).


Historical melanoma survival rates from previous clinical trials have
been estimated by a recent meta-analysis of 42 Phase 2 trials of over
2,100 patients with Stage III or IV metastatic melanoma indicating that,
at one year, approximately 25 percent of patients were alive. Results
from three separately published randomized Phase 3 studies using
dacarbazine as the control arm reported that, at two years,
approximately 8 to 12 percent of metastatic melanoma patients were alive.


The updated survival analyses did not include additional safety data. As
previously reported, safety results include follow-up of up to 16.3
months with a median follow-up ranging from 4.7 to 5.65 months. The most
common immune-related adverse events were rash, diarrhea and hepatitis.
Grade 3 and 4 immune-related adverse event rates were approximately 20
to 29 percent and zero to 12 percent, respectively, in patients who
received 10 mg/kg of ipilimumab. Adverse events were managed with the
use of supportive care and systemic steroids using established treatment
guidelines in the majority of patients. Additionally, the use of
systemic steroids to manage adverse events does not appear to diminish
or impact the clinical effect of ipilimumab (Abstract #9037).


"The ongoing survival data observed with ipilimumab are encouraging,
particularly because the advanced melanoma patient population currently
has limited treatment options," said Steven J. O'Day, M.D., Chief of
Research and Director of the Melanoma Program at The Angeles Clinic and
Research Institute, California. "The potential of ipilimumab is also
underscored by the fact that we can report two-year survival results
from these studies involving a significant number of metastatic melanoma
patients."


Candidate Biomarkers of Ipilimumab

Researchers also presented an exploratory analysis from four Phase 2
ipilimumab studies (008, 022, 007 and 004) that looked at the
association between clinical activity and multiple potential biomarkers,
including the change in absolute lymphocyte count (ALC) in melanoma
patients after they received ipilimumab (Abstracts #9008 and #3020). ALC
is a measure of the number of immune cells in circulation.


In a combined analysis of studies 007, 008 and 022, clinical activity
was associated with an increase in the rate of change in ALC. Patients
with clinical activity had a higher average increase in ALC over time
than did patients without clinical activity (P=0.0013) and no patient
with a decrease in ALC over time had clinical activity. This association
was separately confirmed in Study 004. Increases in ALC following
administration of ipilimumab were also significantly associated with
dose (studies 007, 008, 022: P<0.0001; study 004: P=0.0015), favoring
the 10 mg/kg regimen. Based on these early biomarker findings, further
research to explore the implication of ALC and other potential
biomarkers of clinical activity of ipilimumab continues.


About Studies 008, 022 and 007

The three studies enrolled a total of 487

patients across North
America, Europe, South America, Africa and Australia with Stage III or
Stage IV metastatic melanoma treated with ipilimumab therapy (0.3 mg/kg,
3.0 mg/kg or 10 mg/kg every three weeks for up to four doses, followed
by maintenance dosing every 12 weeks). Specifically, the three Phase 2
monotherapy trials include:


A Phase 2 open-label, single-arm trial (008) evaluating overall
response rate in 155 patients who progressed while on or after
receiving standard treatment;


A Phase 2 randomized, double-blind trial (022) evaluating the efficacy
of three dose levels of ipilimumab in 217 patients who were previously
treated, relapsed or failed to respond to experimental treatment or
were unable to tolerate currently approved therapies; and


A Phase 2 randomized, double-blind trial (007) evaluating the rate of
Grade 2+ diarrhea in 115 patients receiving ipilimumab with or without
prophylactic oral budesonide.


The primary endpoint of studies 008 and 022 was best overall response
rate and the primary endpoint of study 007 was to compare the rate of
Grade 2+ diarrhea in patients receiving ipilimumab with or without
prophylactic oral budesonide. Overall survival, one-year survival rates,
disease control rate, stable disease, and other measurements of
anti-tumor activity and patterns of responses were secondary endpoints
in studies 008, 022 and 007. The two-year survival data reported are
current (through March, 2009) for all subjects followed: 93.6% from
study 008, 91.7% from study 022 and 84.2% and 82.8% from the two
subgroups of study 007 (placebo and budesonide, respectively).


About Study 004

Study 004 is a Phase 2 randomized, double-blind biomarker trial. The
study enrolled 82 patients with advanced melanoma who were previously
treated with therapy other than ipilimumab or who received no prior
therapy. All patients received ipilimumab therapy (3.0 mg/kg or 10
mg/kg). Pre- and post-treatment (week four) tumor biopsies were
performed to assess associations between tumor biomarkers and clinical
activity of ipilimumab. Clinical activity was defined as complete or
partial response or stable disease at ≥24 weeks using modified World
Health Organization criteria.

Thursday, May 14, 2009

Ipilimumab linked to melanoma survival: studies..Melanoma..Jim Breitfeller

Thu May 14, 2009 6:01pm EDT

LOS ANGELES, May 14 (Reuters) - More than a third of advanced melanoma patients treated with ipilimumab, an antibody being developed by Bristol-Myers Squibb Co (BMY.N) and Medarex Inc (MEDX.O), continued to survive after 18 months, according to data released on Thursday.
The 18-month survival rate for three Phase 2 trials ranged from 34.5 percent to 39.4 percent. Most trial participants had been previously treated with other therapies.

"The median survival in the past was only six months," said Renzo Canetta, head of oncology research at Bristol-Myers.

Two-year survival results are slated for presentation later this month at a meeting of the American Society of Clinical Oncology in Orlando.

Bristol-Myers and Medarex said last year that they would delay seeking approval of the experimental treatment after U.S. health regulators asked for additional overall survival data to further demonstrate the benefit of ipilimumab.

Canetta said Phase 3 data for ipilimumab in melanoma patients is expected to mature toward the end of this year or early 2010.

Ipilimumab is a fully human antibody that binds to a molecule on T-cells that plays a critical role in regulating natural immune responses to disease. The drug is also being studied in other tumor types, including lung cancer and prostate cancer.

Source:http://www.reuters.com/article/marketsNews/idUSN1434063520090514


Take care

Jimmy B

Friday, March 27, 2009

Medarex & Bristol-Myers Show Positive Metastatic Melanoma Data Melanoma .Jim Breitfeller

Posted: September 15, 2008 at 9:26 am

There is some very hopeful data out there this morning on cancer survival. Bristol-Myers Squibb Co. (NYSE: BMY) and Medarex, Inc. (NASDAQ: MEDX) have released updated survival data from three Phase II studies of ipilimumab in patients with advanced metastatic melanoma in Stage III or IV levels who had previously been treated showing that approximately half of patients who received ipilimumab remained alive beyond one year.


The results are based on follow-up of the patient population fromstudies 008, 022 and 007 and show a consistent one-year survival ratebetween 47% and 51% as follows:

One-year survival rate of 47% in patients who had progressed while onor after receiving standard treatment (Study 008);follow-up for survival was up to 24.8 months.

One-year survival rate of 48% in patients who were previously treated,relapsed or failed to respond to experimental treatment or were unableto tolerate currently approved therapies (Study 022);follow-up for survival was up to 21.88 months.

One-year survival rate of 51% in patients previously treated withtherapy other than ipilimumab (Study 007); follow-upfor survival was up to 26.32 months.


Jon C. Ogg
September 15, 2008

As you can see, I am not blowing smoke or doing Hat Tricks.

Jimmy B

Friday, February 6, 2009

Delayed Melanoma Response Could Impact Clinical Decisions with Anti-CTLA-4 Agents.. Melanoma..Jim Breitfller

Elsevier Global Medical News. 2008 Nov 7, JS MacNeil

STOCKHOLM (EGMN) - Clinical studies of two experimental agents - tremelimumab and ipilimumab - have shown delayed and mixed responses among patients who gained control of refractory melanomas with these therapies.

Both agents come from a new class of monoclonal antibodies that seek to promote immune response by blocking cytotoxic T-lymphocyte-associated antigen 4 (CTLA-4). In three phase II trials presented at the European Society for Medical Oncology Congress, tremelimumab and ipilimumab ultimately achieved disease control rates of 14%-29% as second-line therapies. No complete responses were reported.

Among patients classified as having progressive disease after ipilimumab treatment, however, were some people who subsequently improved. Likewise, among six patients with "mixed response" to tremelimumab were five patients who initially developed new lesions, but then had slow decreases in targeted lesions. All six were still alive at the time of the presentation.

Investigators suggested that the modified World Health Organization (WHO) criteria used to assess activity of cytotoxic agents may not capture the benefit in some patients classified with progressive disease. They cited four observed patterns of response, which were described in a poster by Dr. Kaan Harmankaya, of the department of dermatology at University of Vienna, and associates:

-Response in baseline lesions.

-Stable disease with a slow, steady decline in tumor volume.

-Response after increase in total tumor volume.

-Response in index and new lesions after the appearance of new lesions.

While delayed response is an issue for researchers, the clinical impact could be more important, according to a discussion of the tremelimumab and ipilimumab studies by Dr. Ulrich Keilholz of the Charité University in Berlin and the European Organisation for Research and Treatment of Cancer melanoma group. In comparing "classical and nonclassical efficacy assessment," he said that nonclassical assessment captures delayed efficacy, but the definitions are complicated and the issues in patient management are distinct from efficacy evaluation in studies.

"Nonclassical assessment does change the response rate, but it does not change the survival rate," Dr. Keilholz said, downplaying the importance of response measures, compared with overall survival in phase III trials.

In clinical practice, however, the physician must decide when to switch a patient from a therapy that is not working. The three trials showed that delayed efficacy does occur with these agents, but the limit appears to be week 20 after treatment, Dr. Keilholz said, adding: "I think that it is important to allow patients a certain amount of time ... but also to put a stop at a certain time point."

Tremelimumab

Dr. John M. Kirkwood, director of the Melanoma Center at the University of Pittsburgh Cancer Institute, presented the tremelimumab data from an open-label phase II trial in 251 patients (nearly all with stage IV disease), of whom 242 were evaluable. The protocol called for a 15 mg/kg dose to be delivered intravenously on the first day of up to four 12-week cycles. Sixteen (7%) patients achieved partial responses and 36 (15%) had stable disease - a clinical benefit rate of 22%.

Dr. Kirkwood said all but 1 of the partial responses lasted at least 170 days, and 11 were ongoing. Median overall survival reached 10.1 months, he said; median progression-free survival reached 2.8 months, with 15.6% of patients progression-free 6 months after treatment. Factors correlating with survival were still being analyzed. The trial was sponsored by Pfizer Inc.

Ipilimumab

The first ipilimumab trial was a multinational, open-label study of 155 patients with advanced disease that had failed previous therapies. Patients received 10 mg/kg of ipilimumab every 3 weeks for four cycles, followed by maintenance therapy at the same dose every 12 weeks from week 12 to week 60.

Dr. Vanna Chiarion Sileni of the Instituto Oncologo Veneto in Padua, Italy, reported 9 patients had partial responses and 33 had stable disease by modified WHO criteria, adding up to a disease control rate of 27% (42/155). The median duration of stable disease was 4.1 months at a median follow-up of 5.7 months, she said; 19 patients were still stable at their last assessment.

Among those classified with progressive disease were patients with the four patterns of response. Small subgroups had a "slow steady decline" in tumor volume after an initial increase in target lesions or the appearance of new lesions, she said.

In the second ipilimumab trial, Dr. Celeste Lebbé of Saint-Louis Hospital in Paris reported on a multinational dose-finding study that randomized patients with unresectable relapsed stage III or IV melanoma to 10 mg/kg, 3 mg/kg, or 0.3 mg/kg of ipilimumab given once every 3 weeks for four cycles followed by maintenance treatment once every 12 weeks.

The 10 mg/kg dose produced the best overall response rate, a composite measure of complete and partial responses, at 11%, and a disease control rate of 29% (the lowest rate, 14%, was at the lowest dose). Nearly half, 48% of 73 patients given the highest dose were alive at 1 year. Their median survival was estimated at 11 months at a median follow-up of 10.4 months.

The four patterns of response were observed in this study as well, Dr. Lebbé reported, and about 35% of patients at the highest dose had a decline in total tumor volume. Patients at this dose also had the most toxicity, she said; about a quarter had grade III adverse events, including gastrointestinal side effects in 16%. In most cases, it was manageable and reversible.

The ipilimumab studies were sponsored by Bristol-Myer Squibb and Medarex Inc, which are jointly developing the agent. Dr. Lebbé was the only investigator to disclose a conflict of interest, having served on two advisory boards for Bristol-Myer Squibb.

Dr. Kirkwood said phase III trials for both agents have been completed and are being analyzed, but applications for approval have not yet been filed. In April 2008, Pfizer halted a phase III study of tremelimumab monotherapy in advanced melanoma when interim data showed it would not be superior to standard therapy.

http://www.oncologystat.com/news-and-viewpoints/news/Delayed_Melanoma_Response_Could_Impact_Clinical_Decisions_with_Anti-CTLA-4_Agents_US.html

Delayed Melanoma Response Could Impact Clinical Decisions with Anti-CTLA-4 Agents


I believe the delayed response was what happen to me.

Jimmy B

Tuesday, February 3, 2009

Trends in Melanoma -----Sanjiv. S. Aqarwala, MD January 29, 2009 Jim Breitfeller

Trends in Melanoma

Sanjiv. S. Aqarwala, MD
January 29, 2009

Sunbelt Melanoma Trial: Final Results
The Sunbelt Melanoma Trial, a multicenter prospective randomized trial, assessed high-dose interferon alfa-2b (IFN) or completion lymph node dissection (CLND) in the treatment of melanoma staged by sentinel lymph node (SLN) biopsy.

Eligible patients 18 to 70 years of age who had primary melanoma with Breslow thickness Ž1.0 mm underwent SLN biopsy and were assigned to one of two protocols. In protocol A, patients with a single positive lymph node after SLN biopsy and CLND were randomized to observation vs high-dose IFN (20 MU/m2/day IV 2 4 weeks followed by 10 MU/m2 /three times per week SC 2 48 weeks). Protocol B included patients with negative SLN determined by standard histopathology and immunohistochemistry. To detect melanoma-specific mRNA, these patients underwent molecular staging of the SLN by RT-PCR. Patients with RT-PCR–positive SLN were randomized to observation vs CLND vs CLND plus IFN (20 MU/m2/day IV 2 4 weeks only).

Randomization was stratified for Breslow thickness and ulceration. The primary end points were disease-free survival (DFS) and overall survival (OS). Intent-to-treat (ITT) and efficacy analyses were performed by Kaplan-Meier and Cox proportional hazards models, and the Data Safety and Monitoring Committee (DSMC) approved the final analysis.

Patients were enrolled between June 24, 1997, and October 31, 2003; median follow-up was 64 months. In the protocol A ITT analysis, there were no significant differences in DFS (HR 0.82; 95% CI, 0.47-1.40; P=0.46) or OS (HR 1.07; CI 0.65-1.78; P=0.79) for patients randomized to IFN (n=112) vs observation (n=106). In protocol B, there were no significant differences in DFS or OS among patients randomized to CLND (n=192; DFS: HR 0.72; CI 0.42-1.23; P=0.23; OS: HR 0.94; CI 0.55-1.59; P=0.81) or CLND plus IFN (n=184; DFS: HR 0.90; CI 0.54-1.50; P=0.69; OS: HR 0.96; CI 0.56-1.63; P=0.88) vs observation (n=180). The efficacy analysis did not demonstrate significant differences in DFS or OS.

This study failed to demonstrate a benefit for adjuvant high-dose IFN for patients with a single positive SLN. In addition, there was no significant benefit to CLND or CLND plus IFN among patients with melanoma cells detected in the SLN by RT-PCR analysis.

Combination Thalidomide Plus Temozolomide in a Phase II Trial in Metastatic Malignant Melanoma (MMM): SWOG S0508
After response rates up to 32% were achieved in single-institution phase II studies of thalidomide plus temozolomide as combination therapy in MMM, some clinicians have used thalidomide plus temozolomide as a standard therapy. This large multicenter phase II trial evaluated the clinical efficacy of this
therapy and the immune modulatory effects of thalidomide when combined with temozolomide in patients with MMM.

Eligible patients had cutaneous MMM proven by biopsy, no active brain metastases, Zubrod PS 0-1, no more than 1 prior systemic therapy for melanoma (excluding thalidomide, temozolomide, or dacarbazine), and adequate organ function. Six-month progression-free survival (PFS) was the primary end point; per study design, if the 6-month PFS rate was 10%, the regimen would not be of interest; if PFS was Ž25%, further study would be warranted. Response rate, OS, toxicities, and assessment of the relationship between immunologic biomarkers and clinical outcomes were secondary end points.

Patients received thalidomide (200 mg/day escalated to 400 mg/day for patients younger than 70 years, or 100 mg/day escalated to 250 mg/day for patients 70 years of age or older) plus concomitant temozolomide (75 mg/m2/day 2 6 weeks with a 2-week rest between cycles). Anticoagulation agents were not required. Treatment was continued until toxicity became unacceptable or disease progressed.

Of the 64 patients enrolled, 2 were ineligible, and 2 refused treatment. The 6-month PFS was 15% (95% CI, 6%-24%), and 1-year OS was 36% (95% CI, 24%-49%). Fifty-one patients had measurable disease by RECIST and were evaluable for response. All responses were partial, at a rate of 14% (95% CI, 6%-26%). One treatment-related death occurred due to MI. Three grade 4 events occurred: one case each of PE, neutropenia, and CNS ischemia; fatigue was the most common of 21 grade 3 events. Immunologic biomarkers were obtained at baseline and at 5, 9, and 13 weeks, including PBMC as a percentage and as an absolute count of CD4+/CD25+/CD69+ and CD16+/CD56+ cells, and ELISPOT reactivity to a recall pool of antigens.

Thalidomide plus temozolomide has little additional clinically meaningful activity compared with temozolomide alone in MMM. In a meta-analysis of systemic therapy for MMM, thalidomide plus temozolomide compared poorly. This regimen should not be considered a standard treatment for MMM.
Clark J, et al. J Clin Oncol. 2008;26(May 20 suppl). Abstract 9007

Unresectable Metastatic Melanoma: A Phase II Clinical Trial With a Second-Generation GM-CSF–
Encoding Oncolytic Herpesvirus
OncoVEX (GM-CSF) is a second-generation oncolytic herpes simplex virus that encodes granulocyte-macrophage colony-stimulating factor (GM-CSF). In a phase I trial, it was well tolerated in patients with several types of tumors, and antitumor effects were seen in both injected and uninjected tumors.
Patients eligible for this phase II trial had unresectable stage IIIc/IV melanoma with Ž1 injectable tumor (ultrasound allowed) and had failed prior therapy. Patients with clinically active brain, liver, or bone metastases were excluded. Fewer than 10 lesions were to be injected, and more than 1 lesion was to be left uninjected. The dosing schedule consisted of one injection of 4 mL of 106 plaque forming units (pfu)/mL split between target tumors, followed 3 weeks later by 24 injections of 108 pfu/mL every 2 weeks. The study was designed to assess single-arm monotherapy in up to 50 evaluable patients, and more than one RECIST response among the first 24 patients was required to continue the trial. Response rate was the primary end point; safety, response kinetics, and survival were secondary end points.

At the time of this report, the study had enrolled 40 patients, 31 of whom were evaluable. Patients had up to 18 injection cycles. By 2 months on therapy, injected tumors routinely responded, often with local complete response (CR); often, palliative benefit was also achieved. Systemic responses included: 3 patients with CR, 3 with partial response (PR), 4 with durable stable disease (SD), and 2 with mixed response (ŽPR of existing disease and ŽPR of lesions, which later became measurable); 2 patients had posttreatment objective responses. Patients with both stage IIIc and IV disease achieved systemic responses, including resolution of visceral disease. Systemic responses are delayed since injected tumor responses take up to 10 months to fully develop. All objective responses have been maintained to date at 4 to 23 months after the first dose, with those patients not achieving CR still on therapy. Side effects have been grade 1 flu-like symptoms.

Data show that 32% of patients achieved CR, PR, or durable SD. Other patients also experienced clinical benefit: 2 patients had response in tumors that were first noted during therapy; 2 patients responded after leaving the study due to progressive disease; additional patients experienced local palliative benefit in otherwise difficult-to-treat tumors. The rate and durability of response is considered impressive compared with other treatments for advanced melanoma, particularly in the second-line/salvage therapy setting, and further evaluation is therefore warranted.

Tremelimumab and Temozolomide or Dacarbazine: A Phase III, Open-Label, Randomized, Comparative Study in Patients With Advanced Melanoma
This phase III study compared OS achieved with tremelimumab, a fully human anticytotoxic T lymphocyte–associated antigen 4 monoclonal antibody, with OS achieved with standard, single-agent chemotherapy.
Eligible patients had unresectable stage IIIc/IV melanoma without brain metastasis, LDH below 2 2 ULN, and no prior systemic treatment for advanced melanoma. Patients were randomized 1:1 to either tremelimumab 15 mg/kg IV every 90 days, or physician's choice of temozolomide 200 mg/m2 po on days 1-5 every 28 days or dacarbazine 1000 mg/m2 IV every 21 days (chemotherapy arm). Primary end point was OS, and secondary end points included response, durable tumor response, 6-month PFS, and safety. Two equally spaced interim analyses were planned based on the group sequential design using the Lan-DeMets alpha and beta spending approach to an O'Brien-Fleming boundary.

Between March 2006 and July 2007, 655 patients enrolled, with 328 patients randomized to tremelimumab (324 treated) and 327 to chemotherapy (319 treated). Significant imbalances were not noted in age, sex, LDH, or disease stage (5% stage IIIc, 15% M1a, 22% M1b, 58% M1c). The most common treatment-related adverse events in the tremelimumab arm were diarrhea (43% overall, 14% grade 3/4), pruritus (25%), and rash (23%). Pituitary or adrenal gland toxicities occurred in 3% of patients, and thyroid toxicities in 4%. There were three treatment-related deaths in the tremelimumab arm but none in the chemotherapy arm.

The independent DSMC advised researchers to end the study on March 28, 2008, because the log-rank test-statistic (P=0.729) had crossed the O'Brien-Fleming futility boundary based on a protocol-specified second interim analysis that reported 340 deaths. The ITT median OS was 11.8 months (95% CI, 10.4-13.9) in the tremelimumab arm and 10.7 months (95% CI, 9.3-12.0) in the chemotherapy arm, with a HR (chemotherapy over tremelimumab) of 1.04 (95% CI, 0.84-1.28).

Tremelimumab as a single agent failed to demonstrate an improvement in OS as a first-line treatment in patients with metastatic melanoma when compared with standard chemotherapy. Analysis of the secondary end points may yield additional information.

Ribas A, et al. J Clin Oncol. 2008;26(May 20 suppl). Abstract LBA9011.

Wednesday, January 28, 2009

April 14, 2008 Pfizer Anti-CTLA4 antibody trial for melanoma stopped for futility ... Jim Breitfeller's point of View

April 14, 2008 Pfizer Anti-CTLA4 antibody trial for melanoma stopped for futility.

"The Data Safety Monitoring Board halted the Phase III randomized open label trial comparing the Pfizer anti-CTLA4 antibody, tremelimumab, to "standard" (and generally ineffective) chemotherapy for metastatic melanoma. The Board has reported that there is no statistical difference between the primary endpoint, overall survival, between the two study arms. Further, statistical analysis reportedly shows that further examination is "futile" or basically unlikely to ever show a statistical difference.

This is a major setback for the hopes of many investigators and patients who felt that the anti-CTLA4 antibodies represent an encouraging potential new therapy for metastatic melanoma, a disease for which there is no universally accepted or generally effective therapy.

Will this completely halt all efforts by Pfizer to develop this drug in melanoma?"

Authored by:
Eric Whitman, MD, is a Medical Director of the Office of Grants and Research for Atlantic Health System in Morristown, New Jersey

The A3671009 Phase III trial in 630 advanced melanoma patients was investigating tremelimumab compared to standard chemotherapy, consisting of dacarbazine and Schering-Plough's Temodar (temozolomide).

I for one, Believe it works but it must be in combination with Interluekin-2. See the Phase III trial was a administered as a single agent.

With my first hand experience, I did one cycle of CTLA-4 therapy and then switched to Interluekin-2. Base on the immune system pathway, the CTLA-4 blockage only activated one signal by attaching to the B7 receptor. It is all in the Medical literature. To get the Immune system to respond, it needs second signal (cell to cell). That is done with IL-2. It is my belief, that there must be time in between therapies to set the pathway and the microenvironment in motion.

I hope Pfizer doesn't give up on this therapy.


Jimmy B

Tuesday, January 27, 2009

Latest survival data from three Phase II ipilimumab studies!!!!! Melanoma ..Jim Breitfeller

Latest survival data from three Phase II ipilimumab studies showed almost half of previously treated metastatic melanoma patients alive beyond one year1,2,3

- Data presented at the 33rd Congress of the European Society for Medical Oncology -


Stockholm – 16 September 2008 – Bristol-Myers Squibb announced updated survival data from three Phase II studies of ipilimumab in patients with advanced metastatic melanoma (Stage III or IV), which showed that approximately half of previously-treated patients who received ipilimumab (10 mg/kg) remained alive beyond one year. 1,2,3 Ipilimumab is designed to block the activity of CTLA-4 (a molecule on T-cells that plays a critical role in regulating natural immune responses), and thereby activates the immune system to fight metastatic melanoma.4,5

The results are based on a follow-up of the patient population from studies 008, 022 and 007. 47 – 51 percent of patients with advanced metastatic melanoma treated with 10 mg/kg of ipilimumab (induction and maintenance) showed a consistent survival rate of one-year.1,2,3 Specifically, the results show:

* 47 percent of patients who had progressed while on or after receiving standard treatment achieved one year survival (Study 008)1

* 48 percent of patients who were previously treated, relapsed or failed to respond to experimental treatment or were unable to tolerate currently approved therapies achieved one-year survival (Study 022)2

* 51 percent of patients previously treated with therapy other than ipilimumab achieved one year survival (Study 007)3

Recent medical literature, based on a meta-analysis of 42 Phase II trials with 2,100 patients, reported a one-year survival rate of approximately 25.5 percent for patients with Stage III or IV metastatic melanoma, the most advanced type of the disease.6

http://www.countrydoctor.co.uk/education/Education%20-%20Metastatic%20melanoma%20hopes.htm

Jimmy B

Tuesday, January 20, 2009

Call for Patients!!!!!!! NEW CLINICAL TRIAL!!!!!!!!

Jim

We have powerful new immunotherapy treatments for patients with metastatic melanoma using cell transfer techniques (see attached publication).

Our latest treatment has a 72% objective response rate with 36% complete responses.

We are currently recruiting patients for our latest trial.


Is there some way to post this “Call for Patients” on the web site?

Steve Rosenberg

Steven A. Rosenberg M.D., Ph.D.

Chief, Surgery Branch
National Cancer Institute
10 Center Drive MSC 1201
CRC Room 3-3940
Bethesda, MD 20892

301-496-4164

sar@nih.gov

Adoptive Cell Therapy for Patients With Metastatic Melanoma: Evaluation of Intensive Myeloablative Chemoradiation Preparative Regimens


Mark E. Dudley, James C. Yang, Richard Sherry, Marybeth S. Hughes, Richard Royal, Udai Kammula,
Paul F. Robbins, JianPing Huang, Deborah E. Citrin, Susan F. Leitman, John Wunderlich, Nicholas P. Restifo,
Armen Thomasian, Stephanie G. Downey, Franz O. Smith, Jacob Klapper, Kathleen Morton,
Carolyn Laurencot, Donald E. White, and Steven A. Rosenberg


Purpose
The two approved treatments for patients with metastatic melanoma, interleukin (IL)-2 and dacarbazine, mediate objective response rates of 12% to 15%. We previously reported that adoptive cell therapy (ACT) with autologous antitumor lymphocytes in lymphodepleted hosts mediated objective responses in 51% of 35 patients. Here, we update that study and evaluate the safety and efficacy of two increased-intensity myeloablative lymphodepleting regimens.

Patients and Method

We performed two additional sequential trials of ACT with autologous tumor-infiltrating lymphocytes (TIL) in patients with metastatic melanoma. Increasing intensity of host preparative lymphodepletion consisting of cyclophosphamide and fludarabine with either 2 (25 patients) or 12 Gy (25 patients) of total-body irradiation (TBI) was administered before cell transfer. Objective
response rates by Response Evaluation Criteria in Solid Tumors (RECIST) and survival were evaluated. Immunologic correlates of effective treatment were studied.

Results

Although nonmyeloablative chemotherapy alone showed an objective response rate of 49%,
when 2 or 12 Gy of TBI was added, the response rates were 52% and 72% respectively.
Responses were seen in all visceral sites including brain. There was one treatment-related death in the 93 patients. Host lymphodepletion was associated with increased serum levels of the lymphocyte homeostatic cytokines IL-7 and IL-15. Objective responses were correlated with the telomere length of the transferred cells.


Conclusion

Host lymphodepletion followed by autologous TIL transfer and IL-2 results in objective responserates of 50% to 70% in patients with metastatic melanoma refractory to standard therapies.

J Clin Oncol 26:5233-5239. Published by the American Society of Clinical Oncology

The paper is upload in my shared files : (see Shared Files)

Dudley JCO '08 Adoptive Cell Therapy for Patients With Metastatic

Friday, January 16, 2009

I Thought I was the Only ONE Seeing This Trend!! Melanoma Jim Breitfeller

Sorry, I tried to catch up on some reading and this was in the pile.
I thought it could not wait. I am Vindicated!!!!

Promising immunotherapeutic approaches to the treatment of metastatic melanoma: modulation of the immune response

Mario Sznol, MD

Yale Cancer Center, New Haven, CT

Durable remissions of advanced unresectable melanoma can be achieved in a small fraction of patients with immune-based therapy, such as high-dose interleukin-2 (IL-2). Based on an increased understanding of normal and pathologic immune responses at the molecular level and the specific interactions between growing tumors and the host immune response, new approaches to cancer immunotherapy are emerging. Optimism for advances in the immunotherapy of melanoma comes from new agents and approaches that specifically target and modify the regulators of T-cell proliferation, survival and effector function, and/or block tumor-related immunosuppressive mechanisms. One of these agents, anti-CTLA4 (anti-cytotoxic T-lymphocyte–associated antigen 4), has shown the ability to produce durable responses in patients with metastatic melanoma, including some previously unresponsive to IL-2. Preclinical studies indicate that even stronger antitumor immune responses can evolve when agents are combined rationally.

Promising immunotherapeutic approaches to the treatment of metastatic melanoma: modulation of the immune response


I shouted FIRE and no one came. Well, now there is two of us Shouting!!!!!


Jimmy B

Metastatic melanoma—challenges for the community oncologist!! Jim Breitfeller

Michael B. Atkins, MD | Beth Israel Deaconess Medical Center, Harvard Medical School, Boston, MA

"The outlook for patients with advanced
melanoma is bleak. Patients with stage IV melanoma have a median
survival of 6–9 months,1–3 with 5-year survival rates of 1%–2%.1,4

An estimated 8,000 Americans will die of melanoma in 2008.1,5 Many of these patients are young, with a median age of ~ 50 years, and otherwise healthy.1,5 This loss of life represents a societal burden in excess
of the actual numbers. Although melanoma is the ninth most common cancer in the United States,1,6 it ranks second among solid tumors in terms of years of productive life lost.

Common treatment approaches have included:
cytotoxic chemotherapy; interleukin-2 (IL-2)–based immunotherapy; and combinations of chemotherapy and immunotherapy (so-called biochemotherapy). Although some treatment approaches, most notably, high-dose IL-2 immunotherapy,
have been shown to produce extremely durable tumor responses in a small percentage of patients,4,7,8 no treatment approach has shown a reproducible survival advantage in phase III trials.

There is a critical need for new treatment approaches for patients with advanced melanoma.Recent advances in the understanding of melanoma
biology, immune regulation, and tumor-induced immune suppression are the foundation for new opportunities to improve therapeutic outcomes for patients with advanced melanoma. Studies of melanoma biology have uncovered critical factors that are important for melanoma cell survival, including activating mutations in BRAF, which occur in > 50% of melanomas; mutations in KIT, the gene encoding the c-Kit receptor, which are common in acral lentiginous and mucosal primary melanomas; overexpression of vascular endothelial growth factor, which drives tumor angiogenesis; and an assortment of factors that limit the apoptotic effects of various cytotoxic chemotherapy agents."

Read the rest:

http://www.oncologystat.com/Images/metastatic_melanoma_tcm8-162554.pdf
Metastatic melanoma—challenges for the community oncologist


Jimmy B

Greetings to One and All

This Blog is dedicated My Brother Kenny B. who passed away in the late 1970's with Cancer before the Internet.

It was he, who showed me How to live and give back. He was wise beyond his years.


Kenny B


Jimmy and Dee

Carepage: Jimmybreitfeller
Jimmy Breitfeller


My Profile as of 2009

My photo
Last July (2005)I was riding my bicycle to work at the Eastman Kodak Research Labs about 3 miles from home. I was wearing a knapsack to carry my things to and from the labs. I started noticing an ache on my back. So I decide to go to the dermatologist. To make the long story short, it was cancer. I knew from my research that I would be needing adjuvant therapy. So I started communicating with Sloan Kettering, University of Pittsburgh Cancer Center, and a couple of others including the Wilmot Cancer Center at Strong. I realized that by telling my story, I might help someone else out there in a similar situation. So to all who are linked by diagnosis or by relation to someone with melanoma, I wish you well. Stay positive, read as much as you can (information helps to eliminate the fear associated with the unknown), and live for today, as no one can predict what tomorrow may bring. Jimmy B. posted 12/15/08

Disclaimer

The information contained within this Blog is not meant to replace the examination or advice of your Oncologist or Medical Team. The educational material that is covered here or Linked to, does not cover every detail of each disorder discussed.

Only your physician/Oncologist can make medical decisions and treatment plans that are appropriate for you. But, An Educated Consumer is a Smart consumer.

As Dr. Casey Culberson Said:

"The BEST melanoma patient is an ACTIVE PARTICIPANT in his or her treatment
(not a PASSIVE RECIPIENT)"

Melanoma and the “Magic Bullet” (Monoclonal Antibodies)

Just to let you know I posted the first draft of the Melanoma and the “Magic Bullet” (Monoclonal Antibodies). on Melanoma Missionary In the Shared File Section. you can download it for 19.95 (Only kidding) it is Free for the taking.


It is 33 pages long and may help you in your quest for the Yellow Brick Broad. Just to let you know it is only the first draft. Revisions are sure to come. I wanted to get it to the people that need it the most, the Melanoma Patients.

Preview:

So, where does Interluekin-2 (IL-2) come into play? According to Byung-Scok et al and recent reports, IL-2 is not needed for developmental CD4+ CD25+ Treg cells in the thymus but does play an important role in the maintenance and function in the peripheral.18 Peripheral is defines as secondary system outside the bone marrow and thymus. It entails the site of antigen, immune system interaction. IL-2 is required for the peripheral generation of Tregs based Abbas’s and colleagues research.19

IL-2 prevents the spontaneous apoptosis of the CD4+ CD25+ Treg cells. It has been reported that patients with multiple advance-stage tumors have elevated levels of Tregs within the tumor microenviroment.20 Interluekin-2 is the survival factor for CD4+ CD25+ Treg cells.21 If the addition of IL-2 is on or before the maximum propagation of the CD4+ T cells, the Tregs population can increase 5-fold in a 96 hour period based on certain growth mediums.

By controlling the addition of the endogenous IL-2, one has a knob to turn and can lead to the control of the expansion of the Tregs. When you combined this control with the anti-CTLA-4 blockage, you can shift the balance of the immune response.

Now here is the catch. The maintenance and function of the CD8+ T-cells require CD4+ cells which secrete IL-2. So we don’t want to deplete the CD4+ cells, we want to control the expansion of the Tregs which are a subset of the CD4+ cells. It has been postulated by some researchers that the Anti-CTLA-4 blockage also suppresses the Treg function in a different mechanism. By using IL-2 as the rate limiting factor, we can suppress the CD4+ CD25+ Treg cell expansion by controlling the concentration and timing of the Inerluekin-2 at the tumor microenvironment.


The Interluekin-2 plays another role in this Melanoma Maze. In a study by Janas et al, Il-2 increases the expressions of the perforin and granzyme A, B and C genes in the CD8+ T-cells. This increase expression causes the CD8+ T-cells to mature into Cytoxic T Lymphocytes (CTLs). The exogenous IL-2 is required for the granzyme proteins. As stated previously, CTLs have cytoplasmic granules that contain the proteins perforin and granzymes. A dozen or more perforin molecules insert themselves into the plasma membrane of target cells forming a pore that enables granzymes to enter the cell. Once in the tumor cell, these enzymes are able to breakup (lyse) the cell and destroy it. This is the beginning of the end for the cancer cells. The tumors begin to shrink and the rest is history,

“

On the other hand, prolong therapy with Il-2 can result in causing apoptotic death of the tumor- specific CD8+ T-cells.23

Clearly in a clinical setting, timing, dose, and exposure to these drugs play a major roll in the immunotherapy, and can have dramatic effects on the outcome.

All it takes is that one magic bullet to start the immune reaction..

https://app.box.com/shared/kjgr6dkztj

Melanoma And The Magic Bullet (Monoclonal Antibodies)

Public Service Announcement

A call for Melanoma Patients by Dr. Steven A Rosenberg

"We continue to see a high rate of clinical responses in our cell transfer immunotherapy treatments for patients with metastatic melanoma", Dr. Rosenberg said.

"We are actively seeking patients for these trials and any note of that on a patient-directed web site would be appreciated."

If you would like to apply for his trials, here is the website and information.

Dr. Rosenberg's information


Dr. Rosenberg's Clinical Trials


For the Warriors


The Melanoma Research Alliance has partnered with Bruce Springsteen, the E Street Band, and the Federici family to alleviate suffering and death from melanoma. Please view Bruce Springsteen’s public service announcement inspired by Danny Federici. Danny was the E Street Band’s organist and keyboard player. He died on April 17, 2008 at Memorial Sloan-Kettering Cancer Center in New York City after a three year battle with melanoma.


http://www.melanomaresearchalliance.org/news/PSA/

Source Fastcures blog


Join the Relay for Life!!!

Photobucket

Dear Family and Friends,

I’ve decided to take a stand and fight back against cancer by participating in the American Cancer Society Relay For Life® event right here in my community! Please support me in this important cause by making a secure, tax-deductible donation online using the link below.

To donate on line now, click here to visit my personal page.
Jimmy B AKA Melanoma_Missionary

Relay For Life® is a life-changing event that brings together more than 3.5 million people worldwide to:

CELEBRATE the lives of those who have battled cancer. The strength of survivors inspires others to continue to fight.

REMEMBER loved ones lost to the disease. At Relay, people who have walked alongside people battling cancer can grieve and find healing.

FIGHT BACK. We Relay because we have been touched by cancer and desperately want to put an end to the disease.

Whatever you can give will help - it all adds up! I greatly appreciate your support and will keep you posted on my progress.

Keep the Fire Burning!!!

Photobucket

Sincerely,

Jimmy Breitfeller
Turn off Music before you "Click to Play"
Signs of Melanoma Carcinoma Skin Cancer

How Skin Cancer Develops by "About.com : Dermatology"

Call for Patients with Unresectable Liver Metastases Due to Melanoma


Delcath Systems Granted Orphan-Drug Designations for Cutaneous and Ocular Melanoma


Delcath is actively enrolling patients in a Phase III clinical trial testing its proprietary drug delivery system, known as Percutaneous Hepatic Perfusion (“PHP”), with melphalan for the treatment of ocular and cutaneous melanoma metastatic to the liver.

This NCI-led trial is enrolling patients at leading cancer centers throughout the United States. Commenting on these orphan-drug designations, Richard L. Taney, President and CEO of Delcath, stated, “These favorable designations are important steps in our efforts to secure Delcath’s commercial position upon conclusion of our pivotal Phase III trial for metastatic melanoma. We remain steadfast in our commitment to become the leader in the regional treatment of liver cancers and we continue to enroll patients in this study, and advance our technology and the promise that it offers to patients with these deadly forms of melanoma and other cancers of the liver, all with limited treatment options.”

Orphan drug designation, when granted by the FDA’s Office of Orphan Products Development, allows for up to seven years of market exclusivity upon FDA approval, as well as clinical study incentives, study design assistance, waivers of certain FDA user fees, and potential tax credits.


Current Trial Centers


Phase I Study of Hepatic Arterial Melphalan Infusion and Hepatic Venous Hemofiltration Using
Percutaneously Placed Catheters in Patients With Unresectable Hepatic Malignancies


James F. Pingpank, Jr., MD, FACS
Associate Professor of Surgery
Division of Surgical Oncology
Suite 406, UPMC Cancer Pavillion
5150 Centre Avenue
Pittsburgh, PA 15232
412-692-2852 (Office)
412-692-2520 (Fax)
PingpankJF@UPMC.edu


Blog Archive

Call For Melanoma Patients!!!!

Call For Melanoma Patients!!!!

Dr. Rosenberg Has a New Clinical Trial.

Our latest treatment has a 72% objective response rate with 36% complete responses.

We are currently recruiting patients for our latest trial.

Is there some way to post this “Call for Patients” on the web site?

Steve Rosenberg

Dr. Rosenberg's Clinical Trials


(For a copy of the research paper.. see My Shared files)

The news headlines shown above for Melanoma / Skin Cancer are provided courtesy of Medical News Today.