Showing posts with label BMY. Show all posts

Thursday, April 23, 2015

Combinatorial Therapy Will Revolutionize Cancer Therapy ...Just wait until ASCO 2015!!


Bristol-Myer Squibb Pharmaceutical Research Institute
Attention: Elliott Sigal
Route 206, Provinceline Road
P.O. Box 4000
Princeton, New Jersey 08543 U.S.A...

 Date: 3-10-2010


Dear Dr. Sigal:
I want to thank you for responding to my emails over the last few months. I know I can be candid and straight to the point sometimes. By reopening the compassionate Drug Use (ipilimumab) you and your company gave the Melanoma Patients “The Last Chance of HOPE”. You don’t know how much this means to us. If we haven’t passed the “Lethal Tumor Burden” we still have a chance of survival. I believe you have done your company justice and showed your compassion. My faith in the Company’s Ethics has been restored.

Now we need to prove to the world that this drug may be one of the most important discoveries in the last twenty years of Cancer. By taking the “Brakes off the Immune System” we can harness our own immune system to battle cancer. Granted we may have to use the drug in combinatorial therapy to rid the host of the cancer once and for all. I hope you and your company can collaborate together with all the major players in this exciting field of Oncology. See it took millions of years for our immune system to evolve, so why do we think that one drug can do it all. We need to approach the Beast arm to arm, to block all the pathways so it can’t escape. This can only be done by using one’s own immune system.

Can you imagine working out a protocol that will vaccinate the patient with the patients own tumor–specific antigen? And Ipilimumab (Anti-CTLA-4 Blockade) is at the center of this revolutionary therapy/protocol. Please if you get a chance, listen to some of the lectures and symposiums from the like of Dr. James Allison, Dr. Jedd Wolchok, Dr. Antonio Ribas, Dr. Jeffery Weber, Dr Keith Flaherty and others. You will be amazed at their accomplishments in the clinical setting. But they need more. They need access to the entire drug arsenal that is available across companies. We now know that timing and dose concentration plays a major roll in setting up an immune response. There are feedback loops. It is like dominos. You have this elaborate step-up. It may take weeks to build. Once you set it in motion, the chips begin to fall. There are different pathways, cytokines, T-cells, receptors, etc that need to be taken into account get the right immune response. This immune response can only be generated if you have all the keys to unlock the response. We need yours and other Pharmaceuticals to work together for the good of the cancer patients. We need to take down all the red tape which also includes the FDA.

“Our Life depends on it.”

Thanks again.
Sincerely,
Jim Breitfeller


“It is not the strongest of the species that survives, nor the most intelligent, but the one most
responsive to change.”

~Charles Darwin~

Take Care,

Jimmy B


Photobucket

Friday, March 27, 2015

The Missing Link in T-cell activation using a Vaccine, "The Danger Signal" may be due to an enzyme called IDO

The Missing Link in T-cell activation using a Vaccine, "The Danger Signal" may be due to an enzyme called IDO

As I research why some patients respond to therapies i.e. vaccination and other immunotherapy and others don’t, I ask WHY? In my quest to get the answer or answers, I came across a paper called “Marked Differences in Human Melanoma Antigen-Specific T Cell Responsiveness after Vaccination Using a Functional Microarray”.

Daniel S. Chen1,2#, Yoav Soen3#, Tor B. Stuge4, Peter P. Lee4, Jeffrey S. Weber5, Patrick O. Brown2,3, Mark M. Davis2,6* 1 Department of Internal Medicine/Division of Oncology, Stanford University, Stanford, California, United States of America, 2 Howard Hughes Medical Institute, Stanford University, Stanford, California, United States of America, 3 Department of Biochemistry, Stanford University, Stanford, California, United States of America, 4 Department of Medicine, Stanford University, Stanford, California, United States of America, 5 Norris Cancer Center, University of Southern California, Los Angeles, California, United States of America, 6 Department of Microbiology and Immunology, Stanford University, Stanford, California, United States of America

This is what I was looking for! It may hold the answer or could possibly point me in the right direction. In the paper I came across a diagram that peaked my interest. It was a comparison between responders and non-responders.


We concluded from these studies that IL-1 and perhaps IL-6 play a critical role in the differentiation and expansion of Th17 cells. Yoshihiro Miyahara et al
 
IL-6 controls Th17 immunity by inhibiting the conversion of naive CD4+ T cells into Foxp3+ regulatory T cells.

Using in vitro and in vivo approaches, we determined that under neutral conditions, simultaneous activation of Tregs and naive CD4+ conventional T cells in the presence of APCs resulted in conversion of Tregs into IL-17–producing cells, and endogenous IL-1β was mandatory in this process according to Vassiliki A. Boussiotis et al. “IL-1β–Mediated Signals Preferentially Drive Conversion of Regulatory T Cells but Not Conventional T Cells into IL-17–Producing Cells”

IL-6 protects CD4 T cells from cell death but also inhibits the suppressive effect of T regs.

“Thus, the addition of IL-6 to the tumor microenvironment skews the balance toward Th17 cells in a murine model of pancreatic cancer. The delayed tumor growth and improved survival suggests that induction of Th17 in the tumor microenvironment produces an antitumor effect.” David C. Linehan  et al

They were looking at the cytokines secreted after the vaccine was given. When I saw what the cytokines were, I knew I was on the right track. These cytokines help in the differentiation of the CD4+ T-cells. What a find!!


Naïve CD4 T cells in the presence of   TGF-b and IL-2 and others differentiate into Tregs.

TGF-b accelerates the CTLA-4 expression by stimulated CD4+ CD25- T-cells

TGF-b requires CTLA-4 early after T-cell activation to induce FoxP expression generating CD4+ CD25+ Treg  Regulatory cells.

The Th-17 cells produce IL-17. .IL-17 induces the production of many other cytokines (such as IL-6, G-CSF, GM-CSF, IL-1β, TGF-β, TNF-α)


So what was the non-responder missing, IL-6.  With the missing IL-6, they weren’t able to produce Th-17 that secreted IL-17.

While TGF-β is a critical differentiation factor for Treg cells, IL6 completely inhibits the generation of Treg cells induced by TGF-β. Instead, IL6 and TGF-β together induce the differentiation of pathogenic Th17 cells. With IL-6 missing in the microenvironment, Treg Cells flourish.

If the CD4 + T cells differentiate into TH2 cells that produce IL-4, the other cells inhibited to produce IL-6. IL-4 was found to inhibit TNF-α and IL-1β by activated monocytes almost 100 %. The Secretion of IL-6 was decreased by approximately 80 % in the presences of IL-4 Cytokine. TE Velde et al 1990

 They were missing “The Danger Signal”.

Friendly inflammation “The Danger Signal”


Most of the time you have no notion of the microbial life-and-death struggle being waged within your body. At other times, though, you are acutely aware of the exact location of the battleground, thanks to the unmistakable signs of inflammation — heat, pain, redness, and swelling. Inflammation, the buildup of fluid and cells at the point of infection/cancer, is put into motion by cytokines — proteins that are released into the blood by the innate immune system when it encounters germs. Cytokines function like police dispatchers. They signal there's a problem, which activates the immune system's highway patrol force: the circulating lymphocytes of the adaptive immune system. These lymphocytes cruise the highways of the blood vessels and lymphatic system. In response to the chemical signal from the cytokines, increased blood flow rushes these circulating cells to the trouble spot.

 “The CD8+ T-cell-mediated Immune Response to Eradicate the Tumors”


 “Three major events must occur to induce CD8+ T cell–mediated, tumor-protective immunity against syngeneic melanoma. First, the T-cell receptor must be triggered by a (or multiple) self antigen–derived peptide MHC class I complex . Therefore, this event depends entirely on appropriate antigen presentation, which is most efficiently provided by mature dendritic cells. Peripherally tolerant or “ignorant” self-reactive T-cell clones, once properly activated, may serve as tumor-specific effector T cells .Second, simultaneously with T-cell receptor triggering, a distinct second costimulatory signal must be delivered, mediated by IL-2, B7-1, or B7-2, which engage IL-2 receptors and CD28 on the surface of the T cell, respectively. A source of these cofactors for effective CD8+ T-cell stimulation can be provided by CD4+ T cells that release critical amounts of IL-2, or by mature dendritic cells that display an increased level of B7-1/B7-2 costimulatory molecules on their cell surfaces. Third, inflammatory cytokines, including IL-1, IL-6, IL-12, IL-17 and IFN-γ provide a third signal that acts directly on T cells, referred to as the “danger signal”. This signal was found to optimally activate TH1 differentiation and lead to clonal expansion of T cells.


The responder was able to produce inflammatory cytokines, including IL-1, IL-6, IL-12, IL-17 and IFN-γ provides a third signal that acts directly on T cells, referred to as the “danger signal”. This signal was found to optimally activate TH1 differentiation and lead to clonal expansion of T cells and invoke a robust immune response to the Melanoma Cancer.


Conclusion:  Based on my observation, the cytokine that ties this “Danger Signal” to the immune system is IL-6.

  • IL-6 protects CD4 T cells from cell death but also inhibits the suppressive effect of Tregs.
  • IL-6 controls Th17 immunity by inhibiting the conversion of naive CD4+ T cells into Foxp3+ regulatory T cells.
So what is causing the lack of IL-6 in the non-responders? The IDO enzyme. This enzyme catalyzes the degradation of the essential amino acid L-tryptophan to N-formylkynurenine.

IDO enzyme degrades tryptophan and through the GCN2 kinase pathway inhibits the transcription of IL-6. Without the transcription of IL-6, the IL-6 cytokine cannot be produced leading to the T-cell differentialtion toward the T Regulatory cell instead of the TH17 phenotype.


My guess is the tumor induced enzyme called IDO may the Missing Link to intiating an immune response.IDO produced by Tumor cells significantly inhibited interleukin (IL-2) expression and proliferative response in T-cells and increased apoptosis (death) of T-cells. Tryptophan depletion is known to halt cell cycle progression by triggering the antiproliferative GCN2 pathway in lymphocytes.

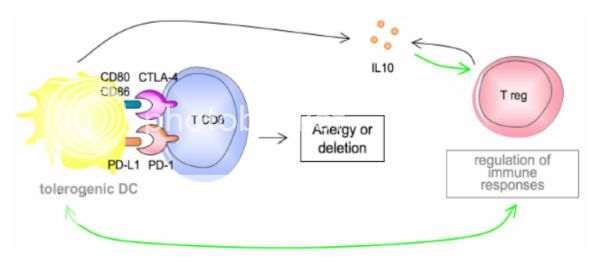
Also, IDO is upregulated in antigen-presenting dendritic cells (DC) by autocrine IFN-γ released as a result of Treg cell–induced CTLA-4/B7-dependent cell-cell signaling.

It is well established that IDO expression by APCs or tumors can inhibit immune responses.

Tryptophan depletion by IDO-expressing tumors is a common mechanism of immune evasion inducing regulatory T cells and inhibiting effector T cells.

So adding IDO inhibitor to a combinatorial therapy like Yervoy for melanoma cancer should see a synergist response.


Bristol Myer Squibb and Incyte Corporation are following this Science along
Newlink.

“It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.” ~Charles Darwin~

Take Care,

Jimmy B

Photobucket

Thursday, May 1, 2014

Immunotherapy.. The Magic Bullet.. The Breakthrough Therapy.. the Paradigm Shift.. The Future

I wrote about this as the "Magic bullet" back in 2009.Great insight in where immunotherapy is heading in the future.


When you combine anti-CD47 therapy with checkpoint therapy (anti-PD1 and or anti-CTLA4/Yervoy), you involve the innate and the adoptive immune system to eradicate cancer (Melanoma)
 I would like to see combinatorial therapy with checkpoint inhibitors like yervoy/anti-CTLA-4 & anti-PD-1along with anti-CD47 to eliminate the "don't eat me" signal, so the macrophages can get involved with the tumor elimination.

http://www.youtube.com/watch?v=XGeqAEr1RnE&feature=share


“It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.” ~Charles Darwin~

Take Care,

Jimmy B
Photobucket

Thursday, January 10, 2013

Pearls of Wisdom: Melanoma ..Jim Breitfeller

Pearls of Wisdom: Melanoma
Reviewed by Douglas Johnson, MD and Jeffrey Sosman, MD

This entry was posted on Tuesday, January 8, 2013 at 6:33 pm Management of Advanced Disease


Metastatic melanoma historically has had a very poor prognosis with a median survival of 6-9 months. However, recent advances in molecularly targeted therapy as well as immune based therapies have provided several effective treatment options for oncologists and their patients. In 2012 there are several important issues to consider in the management of patients with newly diagnosed advanced melanoma.


Advanced Stage III/Stage IV resectable disease

• In patients with advanced stage III disease or oligometastatic disease, consultation with an experienced surgical oncologist is warranted, as patients can experience long term survival with an aggressive surgical approach. Despite the advances in systemic therapy, surgical resection is still our preferred option in most of these clinical situations. One series of 64 patients showed a >30% four year survival in patients who had completely resected metastatic disease.1

•Another option we have offered is a short course of systemic therapy for 6-12 months prior to surgery with the intent to improve the chance that rapid recurrence of disease does not occur and to define the tumor’s responsiveness to the treatment.
•Patients should be considered for clinical trials in the adjuvant setting. Studies are ongoing to assess whether ipilimumab or vemurafenib is effective in preventing recurrences in high risk patients. For stage IV (M1) disease after complete surgical treatment there is no standard of care adjuvant treatment.


•Interferon, the current standard of care for fully resected stage IIb-III disease, is also an option in the adjuvant setting.
Molecular Testing

•All patients with metastatic disease should undergo testing for BRAF V600 mutations given the availability of targeted therapy for this mutation. This should include testing for the alternate V600 mutations that make up about 20% of BRAF mutations at this codon and appear sensitive to the BRAF inhibitors such as vemurafenib and dabrafenib.2 Patients with advanced local or regional disease can also be considered for testing since there are a number of clinical trials either recently or soon to be activated with BRAF inhibitor based therapy in BRAF V600 mutated melanoma at stage IIC-IIIC. Additionally, results will be available on progression so that therapy can be rapidly initiated if needed.
•Evaluation of several KIT mutations should also be considered in at least specific clinically defined subsets of patients. Though KIT mutations are present in only ~2% of all melanomas, acral (feet and hands) and mucosal melanomas harbor KIT mutations in 15-20% of cases. KIT mutations are sensitive to imatinib in about 25% of the cases based on limited numbers of patients.3
•NRAS mutations are also present in 15-20% of patients and though no targeted therapies are yet established as standard for this subset, there are a number of studies underway specifically targeting this mutation. Furthermore, the NRAS mutation may confer a poor prognosis to the melanoma.4


Standard therapies for metastatic disease

Vemurafenib
Vemurafenib is a BRAF inhibitor approved for patients with metastatic melanoma with BRAF V600 mutations (40-50%). In phase III trial data, objective tumor shrinkage was seen in well over 50% of patients, and clinical benefit seen in nearly all patients during the initial few weeks of administration. Median progression-free survival was 6.9 months (compared to 1.6 months with dacarbazine).5 Some important points regarding vemurafenib therapy:
•Responses are often rapid and dramatic. If patients with mutated BRAF V600 melanoma are highly symptomatic, vemurafenib would be our first line therapy in nearly all such patients.
•Patients will inevitably progress or relapse, often within the first year. Strategies to prevent or delay resistance are being pursued. In fact, recently the addition of a MEK inhibitor, trametinib, demonstrated an ability to improve the frequency of objective responses and the duration of progression-free survival in those melanoma patients receiving dabrafenib (BRAF inhibitor).
•Vemurafenib has clinical activity in patients with brain metastases in small series. Prospective phase II trials are pending completion. Trials with dabrafenib have also demonstrated frequent clinical benefits in such patients.6
•Secondary squamous cell carcinomas are common in BRAF inhibitor trials (10-25%).7 Suspicious lesions should be biopsied. Additionally, secondary melanomas and CMML have been reported in the presence of vemurafenib; almost certainly the drug has played a role to accelerate the appearance and growth of these tumors.
Ipilimumab (Yervoy)


Ipilimumab is an antibody to CTLA-4 and functions as an immune checkpoint inhibitor. This “removes the brakes” on the immune system which decreases immune tolerance to the tumor but may also cause autoimmune toxicities. In phase III trials, overall survival was increased compared to a vaccine in previously treated patients (10 mos vs. 6.4 mos), and in combination with dacarbazine compared with dacarbazine alone in the first line setting (11.2 vs. 9.1 months).8,9 Some important points to consider:
•Tumor burden on exam or on imaging may transiently worsen even in patients destined to respond. We do not repeat imaging until after 12 weeks of therapy unless the patient develops concerning new or progressive symptoms.
•Since even responding patients may have tumor growth or slow shrinkage, we are hesitant to use this therapy in highly symptomatic patients, especially if there are reasonable alternatives.
•Autoimmune side effects may be severe. Colitis, hepatitis, dermatitis, neuropathy, and endocrinopathies are the most common toxicities.
•Patients should be monitored closely for colitis. Concerning symptoms (diarrhea, melena/hematochezia, abdominal pain) require rapid evaluation. Though Imodium is appropriate for mild diarrhea (grade I), grade II toxicities or worse require prompt initiation of steroids. Colonoscopy should be performed to confirm the diagnosis in patients with severe colitis. Bowel perforation and death have been reported in extreme cases almost always when initial therapy is delayed.
•Headaches, with or without vision changes and fatigue may represent hypophysitis. Evaluation of TSH, cortisol, and testosterone, and brain MRI can aid in this diagnosis.
•We monitor TSH, cortisol, and liver enzymes at every visit.

•Other rare immune mediated side effects such as Guillan Barre syndrome, myasthenia gravis, sarcoidosis, and hemophilia have also been described.
Interleukin-2 (IL-2)


IL-2 has been used for many years in treating metastatic melanoma. It is associated with 6% durable remission rate (cures) and 15-20% overall response rate.10 Its use is limited to centers familiar with the associated severe side effects. Some points to consider when treating or referring patients:


•Therapy is limited to healthy patients usually under 70 years of age with adequate cardiac, pulmonary, renal, hepatic, and hematopoietic organ function and well controlled brain metastases. Nearly all patients experience treatment associated hypotension, multi-organ dysfunction, and vascular leak syndrome

•Though newer agents exist, IL-2 has the most long term data showing durable remissions in the minority of patients. We still consider this therapy in interested, eligible patients.
•Advantages of using IL-2 compared to ipilimumab include longer duration of use and more rapid assessments of benefit (8 weeks vs. 12+ weeks). Advantages to ipilimumab include outpatient use, generally less severe side effects, and possibly higher rates of durable remissions.


Cytotoxic chemotherapy

•Dacarbazine, temazolamide, and carboplatin/paclitaxel occasionally benefit patients with metastatic disease.
•No consistent survival benefit has been demonstrated with cytotoxic chemotherapy. Response rates are typically in the 5-10% range.
•We use chemotherapy only in patients who are not eligible for other therapies.
Which therapy should be chosen as first line therapy in patients with BRAF V600E/K mutations?
•This decision should be individualized. No head to head comparisons have been done with immunotherapy in the form of ipilimumab or interleukin-2 therapy. BRAF inhibitors are associated with high response rates but inevitable progression, while immune therapies have low objective response rates but durable remissions in a minority of patients.

•In patients with rapidly progressive or highly symptomatic disease, we typically use vemurafenib. In patients with asymptomatic disease, we favor immune based therapies for interested patients. An intergroup randomized cross over trial will address this issue, where half the patients start with vemurafenib and the other half on ipilimumab.


Promising Therapies


Therapy for metastatic melanoma is rapidly evolving. Many clinical trials are ongoing, and patients should be encouraged to participate in clinical trials for first line therapy or at progression if treated with standard therapy options. Some therapies that are likely to be approved are listed below.
•BRAF/MEK inhibitor combination therapies: Dabrafenib (BRAF inhibitor) and trametinib (MEK inhibitor) have both shown benefit individually over dacarbazine in phase III trials in patients with BRAF mutant metastatic melanoma. However, interest lies especially in combination therapy to delay resistance and disease progression. In a randomized phase II trial, combination therapy was associated with an improved objective response rate (54% vs 76%) and progression free survival compared to dabrafenib alone (9.4mo vs. 5.8mo).11 Additionally, the incidence of squamous cell carcinomas was dramatically decreased with combination therapy. Trials are ongoing comparing this combination with vemurafenib in untreated patients with BRAF mutations. An additional trial is evaluating vemurafenib in combination with GDC-0973, a MEK inhibitor.


•Anti-PD-1 therapy:

Several newer checkpoint inhibitors block the interaction between PD-1 (expressed on T-cells) and PD-L1 (expressed on tumor) which activates the immune system, hopefully in a tumor specific manner. A phase I trial with nivolumab (anti-PD1 BMS) data shows a 31% response rate with fewer autoimmune side effects than ipilimumab.12 Pneumonitis was described in several patients. Trials are ongoing in patients who have progressed on ipilimumab. Early reports of another anti-PD1, MK-3475 also show a remarkable response rate in patients either following Ipilimumab or de novo in the 40-50% response range.

•Anti-PD-1 + Yervoy therapy:

By using both Checkpoint inhibitors, you and block two pathways that the melanoma can't use for immunosuppression. This allows the activated T-cells to go unchecked and keeps the immune response switch on. This clinical trial is ongoing at Sloan Kettering, and Yale. Rumor has it that they are seeing high response rates.


References

1.

Sosman JA, Moon J, Tuthill RJ, et al. A phase 2 trial of complete resection for stage IV melanoma: Results of Southwest Oncology Group Clinical Trial S9430. Cancer 2011.
2.

Lovly CM, Dahlman KB, Fohn LE, et al. Routine multiplex mutational profiling of melanomas enables enrollment in genotype-driven therapeutic trials. PloS one 2012;7:e35309.
3.

Carvajal RD, Antonescu CR, Wolchok JD, et al. KIT as a therapeutic target in metastatic melanoma. JAMA : the journal of the American Medical Association 2011;305:2327-34.
4.

Devitt B, Liu W, Salemi R, et al. Clinical outcome and pathological features associated with NRAS mutation in cutaneous melanoma. Pigment cell & melanoma research 2011;24:666-72.


5.

Chapman PB, Hauschild A, Robert C, et al. Improved survival with vemurafenib in melanoma with BRAF V600E mutation. The New England journal of medicine 2011;364:2507-16.     “It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.”
~Charles Darwin~
 Take Care,
Jimmy B
Photobucket

Monday, January 7, 2013

ASCO 2013.. The comming out party for Combination Therapy!!! Yervoy + Anti-PD-1 ..Melanoma. Jim Breitfeller

ASCO 2012 was PD-1’s debutant ball, but we may have found a partner (Yervoy) at this Year’s 2013 Ball and may be only a few years away from its coronation (FDA’s approval) as a stand alone or combinatorial therapy. I believe that ASCO 2013 will be the coming out party for combination therapy of Anti-PD-1 + Yervoy.

br />
Using this combination blocks two checkpoint pathways on the T-Cells leaving it activated to proliferate and destroy the cancer.


If you add Yervoy & Anti-PD-1 to the therapy you have a better chance to activate the CD4 and CD8 T-cells


“It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.”
~Charles Darwin~
Take Care,

Jimmy B

 Photobucket

Friday, September 21, 2012

Legislation for Combinatorial Therapy >> Melanoma ..Jim Breitfeller

Congressman Bilbray, and Congresswomen Maloney and DeLaura are submitting legislation today that, if passed, will provide extended patent protection for investigational drugs that are tested in combination. This will provide a major financial incentive for industry to do the kinds of studies they now find difficult but which offer the best hope for melanoma patients. This legislation came out of meetings MRF had with Congressman Bilbray, whose daughter has Stage III melanoma. We proposed the idea to the Congressman and provided a background document showing how similar action in pediatrics and some infectious diseases has resulted in tremendous progress in drug development. Most doctors agree that real advances in effective treatments will only come through combining two or more drugs together. If these drugs are already approved, doing studies like this are relatively easy. If they are not yet approved--still in clinical trials--they are very difficult. Companies worry that any side effects that arise from a combination study will "taint" the data of their drug and hurt its chances of approval. And they are reluctant to collaborate with other companies on these studies. This legislation will add a "carrot" to the mix and will help accelerate these important studies.
“It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.” ~Charles Darwin~ Take Care, Jimmy B Photobucket

Tuesday, July 3, 2012

Trying to take the guess work out of finding the correct immunotherapy for Melanoma Patients.Jim Breitfeller

As a stage IV survivor/researcher of Melanoma, I know first hand how it feels to be diagnosed with stage IV cancer. You, your family and your caretaker becomes overwhelmed by the information that must be absorbed and processed to make an educated decision on what therapy you want to try. Don’t get me wrong, your oncologist will play a major in your decision, but is it the right one? Is he trying to fill some of his clinical trials or is he looking out for your best interest? Armed with the right information, one can make the best possible choice. It shouldn’t be a hit or miss approach because with cancer, time is of the essence. Getting to the right therapy before you end up at the late stage IV of your disease is the name of the game. In my therapy, that was my goal, find the right therapy before it overcomes your internal organs and kills you. So, in 2005, I asked my doctor John M Kirkwood if they would take my tumors and biopsy them for gene analysis. Back in 2005, this analytical activity was revolutionary and not done as a standard of care. So in 2005, I contacted Arlet Alarcon from the Molecular Profiling Institute. I tried to convince Dr. John M. Kirkwood, but it was not to be. But now to fast-forward to 2012 and you will see molecular profiling your tumor becoming common practice. So with this in mind, here are some suggestions to get you on the right path. 1.) Assemble a team of doctors that specialize in your cancer. 2.) Make sure they see you as a major part of the team and the decision making. (Be your own advocate) 3.) Learn the medical language so you can research and stay abreast of the new therapies that are being discovered daily. 4.) Learn how your immune system works and how the therapies interact with the immune system. 5.) Be POSITIVE!!!
Here is the latest slide from "Evolving Treatment Options in Melanoma: Utilizing Genetic Features to Optimize Therapy" by Dr. Ribas

permission granted from Clinical Care Options – Oncology http://www.clinicaloptions.com/oncology.aspx SOC= Standard of Care
What I am trying tell is that by optimizing your personal therapy, you can extend your survival. “It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.” ~Charles Darwin~ Take Care, Jimmy B Photobucket

Saturday, June 2, 2012

Promising New Approach To Treating Cancer Means Hope For Many, But Remember This Is Just The Start Of The Journey..Melanoma ..Jim Breitfeller

Promising New Approach To Treating Cancer Means Hope For Many, But Remember This Is Just The Start Of The Journey

http://www.cancer.org/AboutUs/DrLensBlog/post/2012/06/02/Promising-New-Approach-To-Treating-Cancer-Means-Hope-For-Many-But-Remember-This-Is-Just-The-Start-Of-The-Journey.aspx


A while back , in 2011 I wrote about combinatorial therapy as the way to form a curative therapy for melanoma.See blog entry "“Schedule and Dose for Combination Therapy,”


It is now just starting to gain acceptance in the oncology world ASCO 2012. You need to block multiple pathways to shutdown the tumor's ability to side-step the immune system.If you search on my blog using the search field, you will be able to follow the science.


“It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.”

~Charles Darwin~

Take Care,

Jimmy B
 Photobucket

Friday, April 27, 2012

Macrophage Activation… The Missing Link to Activation an immune response to Melanoma..Jim Breitfeller


"The development of Th1 cells producing high levels of IFN-gamma could not be induced with dendritic cells alone but required the addition of appropriately activated macrophages." Et al A. O'Gara March 23, 1993 "Dendritic cells and macrophages are required for Th1 development of CD4+ T cells from αβ TCR transgenic mice: IL-12 substitution f.or macrophages to stimulate IFN-γ production is IFN-γ-dependent"
Local IL-12 therapy stimulates Th cells to secrete Th1 cytokines. Exogenous IL-12 application creates an environment rich in IL-12 around the cancer site. In such a local environment, newly activated Th cells, responding to the presence of cancer, exit the blood and are influenced to become Th1 cells and secrete more Th1 cytokines and activate macrophages and NK cells. Activated macrophages will produce more IL-12 and via positive feedback, cell-mediated immunity can be promoted to battle the cancer thereby leading to the prevention of reoccurrence. As you can see, the activated macrophage secretes IL-12, IL-1a, IL-1b, and IL-6 along with a Chemoattractant, IP-10. Without macrophage activation, the immune response does not take place and the patient will relapse.(see graphic below)
With IL-1b and IL-6 missing, the T-Regulatory Cells (Tregs) rule the Tumor's Microenviroment. IL-6 controls Th17 immunity by inhibiting the conversion of naive CD4+ T cells into Foxp3+ regulatory T cells. IL-1β–Mediated Signals Preferentially Drive Conversion of Regulatory T Cells but Not Conventional T Cells into IL-17–Producing Cells (Danger Signal).So if the IL-1b signaling is missing,conversion of the Tregs never take place along with no Danger Signals.
Dr. Steven Rosenberg is using engineered T-cells that secrete IL-12 to stimulate Th cells to secrete Th1 cytokines. This sets in motion the positive feed back loop needed to initiate an immune response. His therapy is show great promise. “It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.” ~Charles Darwin~ Take Care, Jimmy B
Photobucket

Wednesday, April 25, 2012

Interview with Dr. Jim Allison. ..The making of Yervoy..Melanoma..Jim Breitfeller

To Cure cancer, your immune system  must make memory cells that can distingush Melanoma cancer when and if you relapse. This done in at initial stage of T-cell Differentation and propagation. You must have the right Melieu (An environment or a setting) in place. This can be done with Systematic Combinatorial Therapy.
“It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.” ~Charles Darwin~ Take Care, Jimmy B Photobucket

Sunday, April 22, 2012

Thinking outside the Box for the Elderly Melanoma Cancer Patients..Jim Breitfeller

Immunotherapy and Cancer - KTVN Channel 2 - Reno Tahoe News Weather, Video -
New rules of engagement for older patients The body’s immune system does weaken with age, but it also changes, and that changes the rules for fighting disease within the body. Dr. Curiel’s group started by examining an immune therapy that they previously had shown to work in younger hosts, including cancer patients. It’s designed to eliminate regulatory T cells (called Tregs), which are cells that turn off immune responses, allowing cancer to progress. Tregs increase in cancer. In young hosts, the drug turns off Treg activity, allowing the immune system to function better. In older hosts, even though the drug turns off the Tregs, it has no clinical benefit. Dr. Curiel asked the question why, and in this paper his team explains the answer. In older mice, when the drug turned off the Tregs, the researchers found that another type of immune suppressor cell (a myeloid-derived suppressor cell or MDSC) exploded in number to take the Tregs’ place, hampering clinical efficacy. That did not happen in young mice. The team added a second drug that targets the MDSC, and found that with those tools to help immunity, the older hosts can combat cancer just as well as the younger hosts. Adding the second drug afforded no clinical benefit to young hosts, as their MDSC numbers had not increased. “We’ve shown that an aged immune system can combat cancer just as well as a young one if you remove the impediments to successful immunity, which are different than those in younger hosts,” Dr. Curiel said. “We’ve shown that if you test all your immune therapy just in young mice and young people, you’ll never learn how it works in older patients — the ones most at risk for cancer. You might conclude that drugs don’t work in aged hosts, when they do. But they have to be combined with some help.” Human trials on the horizon The next step is to test these concepts in an immune therapy clinical trial for elderly patients, which the research team plans to do, Dr. Curiel said. The drug that is added is anti–Gr-1 antibody and would have to get approval from the FDA, meaning Clinical Trial. With that said, What if we added 5-Fluorouracil to immunotherapy like Yervoy and or Anti-PD1. 5FU immunogenic effects are primarily attributable to MDSC depletion. 5-Fluorouracil selectively kills Tumor-Associated Myeloid-Derived Suppressor Cells Resulting in Enhanced T Cell–Dependent Antitumor Immunity. This would be the one, two punch for elderly cancer patients. Let's Think outside the box. Myeloid-derived suppressor cells (MDSC) have been identified as a population of immature myeloid cells with the ability to suppress T-cell activation in humans and mice. These cells accumulate in the blood, lymph nodes, bone marrow, and at tumor sites in many human cancers and animal tumor models, and inhibit both adaptive and innate immunit. They notably have the capacity to inhibit CD8+ T cell antigen-specific reactivity by different mechanisms, mainly through their capacities to produce nitric oxide and radical oxygen species.


“It is not the strongest of the species that survives, nor most intelligent, but the one most responsive to change.” ~Charles Darwin~ Take Care, Jimmy B Photobucket

Friday, April 13, 2012

I finally have some good news to report!..Julie..Melanoma ..Jim Breitfeller

I finally have some good news to report!

Quick review: Dx Feb 2011 WLE SNLB positive microscopic 1 node. Complete rt groin dissection- rest of nodes negative. Did high dose interferon May 2011, 1 high dose injection then stopped. Surgery July 1 for recurrence at bottom of lymph node scar. Did 4 rounds biochemo- July , august, sep, oct. Recurrence again in same area surgery end November. Started Yervoy end dec had 2 rounds then did radiation to right leg 20 treatments. Finished 4th Yervoy on 2/15/2012.

First PET/CT post Yervoy 02/28/2012 showed "Extensive progression of malignant disease with development of multiple, hepatic, osseous and pulmonary metastatic lesions."

Labs were also awful- LDH got up to 414. Liver enzymes markedly elevated alk phosphatase 374, ast 499, alt 1106.

Labs yesterday-LDH 152 normal!!. Liver enzymes alk phosphotase 142, ast 81, alt, 111 these are still a little high, but markedly improved.
PET/CT: " Very pronounced improvement in metastatic disease. Most of the pulmonary modules noted previously are no longer visible. A few small punctate nodules remain. Only one has identifiable activity on PET portion with < 1 SUV. It measures only a few millimeters. Hepatic metastatic disease has significantly improved. Very significant improvement in skeletal metastatic disease. Many lesions are no longer visible."

Hallelujah!!!!!!!!
Can't stop doing the happy dance.

I'm praying for all to see some improvement in their disease and even a cure.
Hope this post gives some hope to others. I really wonder if the biochemo with IL2 followed by Yervoy along with some radiation is the key to my body finally getting the message.

Julie in Las Vegas

=====================================================================
Julie, Congrats!!!!!

"I really wonder if the biochemo with IL2 followed by Yervoy along with some radiation is the key to my body finally getting the message .".."

You are right on target. The biochem with IL-2 primed your Immune system, while Yervoy deactivated the T-Regs cell suppression of your T-cells. Radiation added the tumor cell debris that is needed to be presented on the Dendritic Cells which are acting as the Antigen Presenting Cells (APCs). The process can be presented in this Diagram.


Remember the this blog. It will lead to a CURE!!! Combinatorial Therapy


“It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.”

~Charles Darwin~

Take Care,

Jimmy B


Photobucket

Thursday, March 8, 2012

New melanoma treatment -- a turning point against cancer? Jim Breitfeller

This is not new!! If you read my paper "Melanoma and the Magic Bullet" from the shared files, you will see that I was able to shed tumor antigens using Chemotherapy.

New melanoma treatment -- a turning point against cancer?

“It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.”

~Charles Darwin~

Take Care,

Jimmy B
Photobucket

Sunday, December 25, 2011

Holiday Wishes to you All !! Melanoma..Jim Breitfeller

I would like to wish each and every one of my carepage friends the warmest and deepest greetings this Holiday Season. We been through a lot and with the comfort of family and friends we can beat the Beast Melanoma.

It has been truely a renewed emergence in Melanoma therapy this past year with TWO therapies being FDA approved that extends survival for us Melanoma patients. At this time of the Season, please relect on the Worriors that are no longer with us, but made this all possible by offering their life to the progress of science.

They truely have shown us the gift of giving.

They truely are my/our HEROS!!!

We will miss them dearly.

Happy Holidays


“It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.”

~Charles Darwin~

Take Care,

Jimmy B

Photobucket

Thursday, July 14, 2011

After Activation With Yervoy, IL-2 Produced by Activated CD4+ T Cells Helps CD8+ T-Cell Activation.Melanoma..Jim Breitfeller

YERVOY™ (Ipilimumab) Approved For The Treatment Of Previously-Treated Advanced Melanoma In The EU
Posted 6 minutes ago
Article Date: 14 Jul 2011 - 4:00 PDT

Bristol-Myers Squibb today announced that the European Commission has approved YERVOY™ (ipilimumab) for the treatment of adult patients with previously-treated advanced melanoma.


After Activation With Yervoy, IL-2 Produced by Activated CD4+ T Cells Helps CD8+ T-Cell Activation.

IL-2 Is Critical to CD8+ T Cell Activation at Early Time Points during Priming.

combination therapy


The Action of IL-2 on CD8+ T Cells Is through IL-2 Receptor
IL-2 signals to naïve CD8+ T cells through IL2 Receptor

It is hypothesized that IL-2 may help CD8+ T cell activation through enhancing the signal that drives proliferation.


IL-2 Signaling during Priming Helps CD8+ T Cells Acquiring Effector Functions,


Generation of Potent CD8+ T Cell Anti-Tumor Effector Function Depends upon IL-2 Help.


IL-2 signal at priming drove better anti-tumor CTL function in vivo.

This is why Combinatorial Therapy is a Must to CURE Melanoma

Yervoy (Ipilimumab) + IL-2 = Melanoma CURE!!!!

You must get the tumors's microenviroment in the right configuration for it to work.


“It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.”

~Charles Darwin~
Take Care,

Jimmy B

Photobucket

Friday, June 24, 2011

Yervoy.. The Magic Bullet!!..Melanoma..Jim Breitfeller

Hi everyone

I´ve been reading posts at this Bulletin Board for almost a year now. Some posts I have read with tears in my eyes, and some with joy. Here is our story (short version):

I am the husband to a 39 year old woman from Denmark in Europe.

In 2003 she had a mole removed from her thigh (Stage II). It contained melanoma-cells.

In 2007 melanoma had spread to a lymph-node in her groin (Stage III). Surgery was needed.

In 2008 melanoma relapsed in another lymph-node, surgery again.

In 2009 melanoma hit us hard (Stage IV). It had spread to her lungs, one met in each lung. The size of the mets was 25 mm and 16 mm respectively. Surgery was fortunately possible.

In October 2010 melanoma went back. This time there was multiples mets in each lung. About 5-6 mets in each lung. The biggest was 19 mm. It was unsurgeable, which was very hard to cope with.

In November she began Interferon/Interleukin-2 treatment. It was tough beyond imagination. She had all the known sideeffects, and she was so bad during hospitalization. The midway PET/CT scans in January revealed that she was a responder! Scans showed that all the mets had become inactive or necrotic. Some mets had even shrunk a little bit. We were delighted, and she continued with the third and fourth series of Interferon/IL-2.

February 15 we got the results of the next scan. We were optimistic because the midway scans was indeed promising. We were shocked when told that the melanoma had began to grow again. There was 2 active mets now. One big met, about 32 mm in diameter, in her right lung lightened up. In addiction there was a lot of fluid in the right lung membrane, and it probably contained melanoma-cells. All other mets was still inactive, except one, and our doctor feared that it would be only a matter of time, before the other mets would begin to grow again. We were devastated.

Our doctor suggested Ipilimumab, and my wife started March 11, on the same day Japan was shaken by the huge earthquake. I watched it on TV while she was receiving the first dose of ipilimumab (3 mg/kg dose). I remember wishing that the drug was the earthquake of our lives…

My wife have always been a positive and happy human being, no matter what challenges life would bring, she still truly believe that she could defeat this Melanoma Devil. She began consulting a Chinese doctor and received acupuncture twice a week. Beside this she trained 4-5 times a week, fitness and running. In these situations we talked about preparing your body to fight the cancer, with a "little" help from our friend, ipilimumab…

She received 4 doses every third week and got a CT scan in June.

Three days ago on June 21 we arrived to the hospital to talk with our doctor about the results of the CT scan. The time from the scans being done and to get the results is awful with a lot of anxiety, you guys all know… The scan showed that the 32 mm met in the right lung was completely GONE!!!!! The fluid was gone too, and the x-ray showed a nice healthy looking right lung. We were stunned. I hugged my wife with a lot of tears in my eyes. Our doctor was very delighted too. Ipilimumab had worked much better than expected. We had hoped for stabilization, maybe shrinkage, if we were lucky. But this???? Unbelievable. Some other small mets was still there but hasn´t grown in size in half a year, and our doctor said it very well could be necrotic tissue.

This is where we stand now. We´re thrilled and delighted and so so happy. We have now dared to plan for more than a month :-)

So this story is to all you Warriors out there, keep on fighting with believe and trust in your hearts. The path is very tough but the battle can be won, sooner or later. We´ll keep fighting this Devil.


Kind regards

willtolive

========================================================================


Did High Dose Interferon Alpha set the stage for the perfect Orchestration of an Immune Response?

As I continue my search for the Holy Grail, I need to keep grounding myself to what really took place in the Melanoma treatment. I can not keep wondering if Interferon therapy had played a part in our successful treatment.

Both Vicky and I did some IFN therapy first.


Vicky’s Treatment timeline:

1) Diagnosis 5/10/06
2) Excision and sentinel node biopsy 5/16/06. SN positive, MM 3.3 mm, amelanotic, ulcerated (I did just read that the ulcerated variant does seem to do well with high-dose interferon in terms of prolonging survival)
3) Elective radical lymph node dissection, right groin, 5/30/06 2 more positive lymph nodes
4) High-dose iv interferon all of July 2006, followed by subcutaneous interferon MWF for 2 months.
5) Enroll in anti-CTLA-4 study as adjuvant therapy for stage 3 MM with Dr. Jeffrey Weber at USC. First dose of intravenous infusion of anti-CTLA-4, dose of 10 mg/kg early Nov 2006, second dose was Jan. 9, 2007.
6) Chest CT, routine, for the study, was positive for bilateral pulmonary nodules on 1/18/07
7) Lung biopsy positive for MM on 2/03/07
8) First course of high-dose IL-2 was March 2007
9) 60% reduction in tumor burden on April 23 CT scans
10) Second course of IL-2 in June 2007 ( I believe I got 14 of 14 doses during the 3rd cycle or week 1 of the second course.
11) Complete response seen on CT 8/01/07
12) Took an elective 5th cycle of IL-2 in early September of 2007- got quite sick and stopped. I think I got around 9 doses that last time.


Did High Dose Interferon Alpha set the stage for the perfect Orchestration of an Immune Response?


“It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.”

~Charles Darwin~

Take Care,

Jimmy B

Photobucket

Tuesday, June 14, 2011

2011 ASCO Annual Meeting Highlights on Melanoma and Neuroblastoma, with Lynn Schuchter, MD ..jim breitfeller

2011 ASCO Annual Meeting Highlights on Melanoma and Neuroblastoma, with Lynn Schuchter, MD
June 5, 2011

2011 ASCO Annual Meeting Highlights on Melanoma and Neuroblastoma, with Lynn Schuchter, MD


“It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.”

~Charles Darwin~

Take Care,

Jimmy B

Photobucket

Thursday, June 2, 2011

Bristol, Roche team up on melanoma study..Jim Breitfeller

By Bill Berkrot and Lewis Krauskopf

NEW YORK | Thu Jun 2, 2011 1:30pm EDT

NEW YORK (Reuters) - Bristol-Myers Squibb and Roche Holding AG said on Thursday they would evaluate their respective cancer drugs as a potential combination therapy for metastatic melanoma.

The collaboration involves a Phase I/II study with Bristol's recently approved Yervoy and Roche's experimental drug, vemurafenib, to determine the safety and efficacy of the combination in treating the deadliest form of skin cancer.

The announcement comes as the American Society of Clinical Oncology meeting begins this weekend in Chicago, where emerging treatments for melanoma will be in the spotlight.

Among the most eagerly anticipated studies being presented at the ASCO meeting will be a Phase III trial intended to show that vemurafenib extended the lives of patients with advanced melanoma, and another study comparing Yervoy to chemotherapy in patients with the fatal disease.

Yervoy won U.S. approval in March for patients with inoperable or metastatic melanoma, making it the first new treatment option in many years for patients for whom there was little hope and virtually no effective medicines.

Roche and Japanese drugmaker Daiichi Sankyo Co recently submitted U.S. and European applications seeking approval for vemurafenib. The drug was developed by Roche's Genentech unit and Plexxikon, which was recently acquired by Daiichi.

Vemurafenib, a so-called BRAF inhibitor, is designed to selectively target and inhibit a mutated form of the BRAF protein found in about half of all cases of melanoma. The combination study with Yervoy will be in patients with BRAF-mutated metastatic melanoma, Roche said.

Roche is also developing a combination diagnostic to help identify those patients with the BRAF mutation who are likely to benefit from vemurafenib.

"We are entering a new era for melanoma, and are committed to studying exciting combinations with investigational medicines in our own pipeline," Roche Chief Medical Officer Hal Barron said in a statement.

If proven effective and approved the Yervoy-vemurafenib combination would be an extremely expensive treatment option that could meet with reimbursement resistance from government programs and health insurers.

Bristol priced a four-infusion course of Yervoy at about $120,000. Vemurafenib will likely also command premium pricing if it too demonstrates an ability to help patients live longer.

More than 70,000 people in the United States and 160,000 worldwide are diagnosed with melanoma each year, according to the American Cancer Society. The five-year survival rate for the aggressive cancer is just 15 percent.

Source:http://www.reuters.com/article/2011/06/02/us-bristol-roche-melanoma-idUSTRE75151W20110602


All I can say.... It is about Time!!!! Lets all work together for the common good.


“It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.”
~Charles Darwin~

Take Care,

Jimmy B

Photobucket

Wednesday, May 11, 2011

Ipilimumab and Beyond: New Therapies Imminent in Melanoma..Jim Breitfeller

Ipilimumab and Beyond: New Therapies Imminent in Melanoma
By: SUSAN LONDON, Internal Medicine News Digital Network


05/11/11
LAS VEGAS – Melanoma has the fastest-rising incidence of any cancer, and exacts a terrible toll among individuals who are typically in the prime of their life. But historically, it has not been a major focus in oncology, in part because of its propensity to metastasize early and the very limited treatment options when it does.

This is changing – and not just because of the landmark clinical trial showing that ipilimumab (Yervoy) can prolong the lives of these patients, Dr. Steven O’Day, a lead investigator of that trial, told attendees at the annual Community Oncology Conference


Ipilimumab targets the immune system so that it can contain the cancer, rather than targeting the tumor to eradicate the disease, explains Dr. Steven O'Day.


Four new classes of therapies are improving outcomes in patients with metastatic melanoma, according to Dr. O’Day, director of the melanoma program at the Angeles Clinic and Research Institute in Santa Monica, Calif.

The rest can be viewed at Internal Medicine News


Remember:Ipilimumab and Beyond!!!!

You heard it first back in 2006 right here. It may not be a cure, but it is a durable response that can last for YEARS!!!

With combinatorial therapy, the response rate will improve greatly.


“It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.”
~Charles Darwin~

Take Care,
Jimmy B

Photobucket

Thursday, February 24, 2011

A Melanoma Story,.. Read the Comments. BMS denies Compassionate Care to a dying patient.. Jim Breitfeller

A Melanoma Story,.. Read the Comments. BMS denies Compassionate Care to a dying patient. It is an EYE OPENER!!!!!!

-And-thats-all-I-know


Read the 62+ comments from the comments link at the top of the page.

Bristol Myer Squibb should be held accountable for it's actions.

“It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.”
~Charles Darwin~
Take Care,
Jimmy B
Photobucket

Greetings to One and All

This Blog is dedicated My Brother Kenny B. who passed away in the late 1970's with Cancer before the Internet.

It was he, who showed me How to live and give back. He was wise beyond his years.


Kenny B


Jimmy and Dee

Carepage: Jimmybreitfeller
Jimmy Breitfeller


My Profile as of 2009

My photo
Last July (2005)I was riding my bicycle to work at the Eastman Kodak Research Labs about 3 miles from home. I was wearing a knapsack to carry my things to and from the labs. I started noticing an ache on my back. So I decide to go to the dermatologist. To make the long story short, it was cancer. I knew from my research that I would be needing adjuvant therapy. So I started communicating with Sloan Kettering, University of Pittsburgh Cancer Center, and a couple of others including the Wilmot Cancer Center at Strong. I realized that by telling my story, I might help someone else out there in a similar situation. So to all who are linked by diagnosis or by relation to someone with melanoma, I wish you well. Stay positive, read as much as you can (information helps to eliminate the fear associated with the unknown), and live for today, as no one can predict what tomorrow may bring. Jimmy B. posted 12/15/08

Disclaimer

The information contained within this Blog is not meant to replace the examination or advice of your Oncologist or Medical Team. The educational material that is covered here or Linked to, does not cover every detail of each disorder discussed.

Only your physician/Oncologist can make medical decisions and treatment plans that are appropriate for you. But, An Educated Consumer is a Smart consumer.

As Dr. Casey Culberson Said:

"The BEST melanoma patient is an ACTIVE PARTICIPANT in his or her treatment
(not a PASSIVE RECIPIENT)"

Melanoma and the “Magic Bullet” (Monoclonal Antibodies)

Just to let you know I posted the first draft of the Melanoma and the “Magic Bullet” (Monoclonal Antibodies). on Melanoma Missionary In the Shared File Section. you can download it for 19.95 (Only kidding) it is Free for the taking.


It is 33 pages long and may help you in your quest for the Yellow Brick Broad. Just to let you know it is only the first draft. Revisions are sure to come. I wanted to get it to the people that need it the most, the Melanoma Patients.

Preview:

So, where does Interluekin-2 (IL-2) come into play? According to Byung-Scok et al and recent reports, IL-2 is not needed for developmental CD4+ CD25+ Treg cells in the thymus but does play an important role in the maintenance and function in the peripheral.18 Peripheral is defines as secondary system outside the bone marrow and thymus. It entails the site of antigen, immune system interaction. IL-2 is required for the peripheral generation of Tregs based Abbas’s and colleagues research.19

IL-2 prevents the spontaneous apoptosis of the CD4+ CD25+ Treg cells. It has been reported that patients with multiple advance-stage tumors have elevated levels of Tregs within the tumor microenviroment.20 Interluekin-2 is the survival factor for CD4+ CD25+ Treg cells.21 If the addition of IL-2 is on or before the maximum propagation of the CD4+ T cells, the Tregs population can increase 5-fold in a 96 hour period based on certain growth mediums.

By controlling the addition of the endogenous IL-2, one has a knob to turn and can lead to the control of the expansion of the Tregs. When you combined this control with the anti-CTLA-4 blockage, you can shift the balance of the immune response.

Now here is the catch. The maintenance and function of the CD8+ T-cells require CD4+ cells which secrete IL-2. So we don’t want to deplete the CD4+ cells, we want to control the expansion of the Tregs which are a subset of the CD4+ cells. It has been postulated by some researchers that the Anti-CTLA-4 blockage also suppresses the Treg function in a different mechanism. By using IL-2 as the rate limiting factor, we can suppress the CD4+ CD25+ Treg cell expansion by controlling the concentration and timing of the Inerluekin-2 at the tumor microenvironment.


The Interluekin-2 plays another role in this Melanoma Maze. In a study by Janas et al, Il-2 increases the expressions of the perforin and granzyme A, B and C genes in the CD8+ T-cells. This increase expression causes the CD8+ T-cells to mature into Cytoxic T Lymphocytes (CTLs). The exogenous IL-2 is required for the granzyme proteins. As stated previously, CTLs have cytoplasmic granules that contain the proteins perforin and granzymes. A dozen or more perforin molecules insert themselves into the plasma membrane of target cells forming a pore that enables granzymes to enter the cell. Once in the tumor cell, these enzymes are able to breakup (lyse) the cell and destroy it. This is the beginning of the end for the cancer cells. The tumors begin to shrink and the rest is history,

“

On the other hand, prolong therapy with Il-2 can result in causing apoptotic death of the tumor- specific CD8+ T-cells.23

Clearly in a clinical setting, timing, dose, and exposure to these drugs play a major roll in the immunotherapy, and can have dramatic effects on the outcome.

All it takes is that one magic bullet to start the immune reaction..

https://app.box.com/shared/kjgr6dkztj

Melanoma And The Magic Bullet (Monoclonal Antibodies)

Public Service Announcement

A call for Melanoma Patients by Dr. Steven A Rosenberg

"We continue to see a high rate of clinical responses in our cell transfer immunotherapy treatments for patients with metastatic melanoma", Dr. Rosenberg said.

"We are actively seeking patients for these trials and any note of that on a patient-directed web site would be appreciated."

If you would like to apply for his trials, here is the website and information.

Dr. Rosenberg's information


Dr. Rosenberg's Clinical Trials


For the Warriors


The Melanoma Research Alliance has partnered with Bruce Springsteen, the E Street Band, and the Federici family to alleviate suffering and death from melanoma. Please view Bruce Springsteen’s public service announcement inspired by Danny Federici. Danny was the E Street Band’s organist and keyboard player. He died on April 17, 2008 at Memorial Sloan-Kettering Cancer Center in New York City after a three year battle with melanoma.


http://www.melanomaresearchalliance.org/news/PSA/

Source Fastcures blog


Join the Relay for Life!!!

Photobucket

Dear Family and Friends,

I’ve decided to take a stand and fight back against cancer by participating in the American Cancer Society Relay For Life® event right here in my community! Please support me in this important cause by making a secure, tax-deductible donation online using the link below.

To donate on line now, click here to visit my personal page.
Jimmy B AKA Melanoma_Missionary

Relay For Life® is a life-changing event that brings together more than 3.5 million people worldwide to:

CELEBRATE the lives of those who have battled cancer. The strength of survivors inspires others to continue to fight.

REMEMBER loved ones lost to the disease. At Relay, people who have walked alongside people battling cancer can grieve and find healing.

FIGHT BACK. We Relay because we have been touched by cancer and desperately want to put an end to the disease.

Whatever you can give will help - it all adds up! I greatly appreciate your support and will keep you posted on my progress.

Keep the Fire Burning!!!

Photobucket

Sincerely,

Jimmy Breitfeller
Turn off Music before you "Click to Play"
Signs of Melanoma Carcinoma Skin Cancer

How Skin Cancer Develops by "About.com : Dermatology"

Call for Patients with Unresectable Liver Metastases Due to Melanoma


Delcath Systems Granted Orphan-Drug Designations for Cutaneous and Ocular Melanoma


Delcath is actively enrolling patients in a Phase III clinical trial testing its proprietary drug delivery system, known as Percutaneous Hepatic Perfusion (“PHP”), with melphalan for the treatment of ocular and cutaneous melanoma metastatic to the liver.

This NCI-led trial is enrolling patients at leading cancer centers throughout the United States. Commenting on these orphan-drug designations, Richard L. Taney, President and CEO of Delcath, stated, “These favorable designations are important steps in our efforts to secure Delcath’s commercial position upon conclusion of our pivotal Phase III trial for metastatic melanoma. We remain steadfast in our commitment to become the leader in the regional treatment of liver cancers and we continue to enroll patients in this study, and advance our technology and the promise that it offers to patients with these deadly forms of melanoma and other cancers of the liver, all with limited treatment options.”

Orphan drug designation, when granted by the FDA’s Office of Orphan Products Development, allows for up to seven years of market exclusivity upon FDA approval, as well as clinical study incentives, study design assistance, waivers of certain FDA user fees, and potential tax credits.


Current Trial Centers


Phase I Study of Hepatic Arterial Melphalan Infusion and Hepatic Venous Hemofiltration Using
Percutaneously Placed Catheters in Patients With Unresectable Hepatic Malignancies


James F. Pingpank, Jr., MD, FACS
Associate Professor of Surgery
Division of Surgical Oncology
Suite 406, UPMC Cancer Pavillion
5150 Centre Avenue
Pittsburgh, PA 15232
412-692-2852 (Office)
412-692-2520 (Fax)
PingpankJF@UPMC.edu


Blog Archive

Call For Melanoma Patients!!!!

Call For Melanoma Patients!!!!

Dr. Rosenberg Has a New Clinical Trial.

Our latest treatment has a 72% objective response rate with 36% complete responses.

We are currently recruiting patients for our latest trial.

Is there some way to post this “Call for Patients” on the web site?

Steve Rosenberg

Dr. Rosenberg's Clinical Trials


(For a copy of the research paper.. see My Shared files)

The news headlines shown above for Melanoma / Skin Cancer are provided courtesy of Medical News Today.