Showing posts with label CTL. Show all posts

Tuesday, October 19, 2010

Dilated capillaries at the melanoma tumor’s microenvironment caused by inflammation cytokines is the beginning of the “Danger Signals”.Jim Breitfeller


Three major events must occur to induce CD8+ T cell–mediated, tumor-protective immunity against melanoma.


First, the T-cell receptor must be triggered by a (or multiple) self antigen–derived peptide MHC class I complex. Therefore, this event depends entirely on appropriate antigen presentation, which is most efficiently provided by mature dendritic cells. Peripherally tolerant or “ignorant” self-reactive T-cell clones, once properly activated, may serve as tumor-specific effector T cells.

Second, simultaneously with T-cell receptor triggering, a distinct second costimulatory signal must be delivered, mediated by IL-2, B7-1, or B7-2, which engage IL-2 receptors and CD28 on the surface of the T cell, respectively (17). A source of these cofactors for effective CD8+ T-cell stimulation can be provided by CD4+ T cells that release critical amounts of IL-2, or by mature dendritic cells that display an increased level of B7-1/B7-2 costimulatory molecules on their cell surfaces.

Third, inflammatory cytokines, including IL-1, IL-6, IL-12, and IFN-γ provide a third signal that acts directly on T cells, referred to as the “danger signal”. This signal was found to optimally activate TH1 differentiation and lead to clonal expansion of T cells.1


The inflammatory cytokines act to promote T cell responses. They include IL-1, IL-6, IL-12, TNF-α, and IFN-g produced by macrophages and/or dendritic cells. Th17 cells also plays a part by secreting IL-17 and others. The most notable role of IL-17 is it involvement in inducing and mediating proinflammatory responses. Neutrophils are the earliest cells to arrive at the inflammatory site.

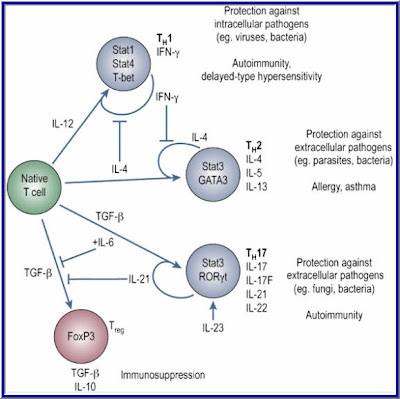
While TGF-β is a critical differentiation factor for Treg cells, IL6 completely inhibits the generation of Treg cells induced by TGF-β. Instead, IL6 and TGF-β together induce the differentiation of pathogenic Th17 cells. With IL-6 missing in the microenvironment, Treg Cells flourish.

If the CD4 + T cells differentiate into TH2 cells that produce IL-4, the other cells inhibited to produce IL-6. IL-4 was found to inhibit TNF-α and IL-1β by activated monocytes almost 100 %. The Secretion of IL-6 was decreased by approximatly 80 % in the presences of IL-4 Cytokine. TE Velde et al 1990


Neutrophil recruitment can also be induced by cytokines such as IL-17 and Tumor necrosis factor (TNF). Among the family of IL-17 cytokines, IL-17A and IL-17F are able
to promote the recruitment of monocytes and neutrophils via the induction of other cytokines and chemokines such as G-CSF and IL-8 by various cell types.

IL-17 appears to be involved in promoting neutrophil influx into the tumor site. With the influx of neutrophils in the tumor’s microenvironment and the inflammatory cytokines, capillaries at the melanoma tumor’s microenvironment become dilated, making room for the recruitment of immune cells.

Neutrophils also play an important role in promoting or suppressing the Th1 immune response, which is mediated partly by induction of cytokines or chemokines. Depending on the compositional makeup of the microenvironment, the neutrophils can promote the right immune response. Studies revealed that these neutrophils secreted three different chemokines. Some of these chemokines are known as chemoattractants. A chemoattractant is a chemical (chemotactic) agent that induces an organism or a cell, a leukocyte, to migrate toward.


These chemokines, MIP-1alpha, MIP-1beta, and MCP-1 are recently reported to serve as chemoattractants for Th1 cells. MIP-1alpha and MCP-1 are also reported to enhance antigen-specific (CTL) Cytotoxic T Lymphocyte induction. Studies revealed that MIP-1alpha /beta released from neutrophils are involved in recruitment of macrophages, T cells, monocytes, dendritic cells (DC), neutrophils and NK cells.
MIP-1 attracts predominantly CD8+ T cells while MIP-1 attracts CD4+ cells, although there is some overlap between subsets in response to both chemokines.

The other Chemokine MCP-1, binds to CCR2 to accumulate monocytes/macrophages, DC, T cells, and NK cells, thereby playing an important role in innate and adaptive immunity. CCR2 is Chemokine receptor that is key determinant of leucocyte trafficking.
IL-2 strongly upregulates expression of CCR2. With the MCP-1/CCR2 interface, the cells can traffic towards the tumor’s microenvironment. The trafficking of the cells and inflammatory cytokines present the perfect storm in the tumor’s microenvironment to induce the right immune response to eradicate the cancer, Melanoma.


Neutrophils circulate in the bloodstream and must be signaled to leave the bloodstream and enter tissues. The signal often comes from the bacteria themselves, from complement proteins, or from damaged tissue, all of which produce substances that attract neutrophils to a trouble spot. (The process of attracting cells is called chemotaxis.)


The combination of chemoattractants and inflammatory cytokines, in the tumor’s microenvironment, helps to send out a Danger Signal which in turn invokes the right immune response to eradicate the Melanoma tumors.


“It is not the strongest of the species that survives, nor the most intelligent, but the one most responsive to change.”
~Charles Darwin~

Take Care,

Jimmy B
Photobucket

Thursday, March 25, 2010

Déjà vu.. Blame it on the Tregs!! Melanoma..Jim Breitfeller

Déjà vu.. Blame it on the Tregs!!!!!!

As I reevaluate my theory, I have come full circle in my research and came across the research paper entitled:
The Role of Regulatory T Cells in Cancer
Tai-You Ha*
Department of Immunology, Chonbuk National University Medical School, Chonju, Chonbuk, Korea

The Role of Regulatory T Cells in Cancer


I postulate that the T regulatory cells may be the major stumbling block in the whole immunotherapy.
Recent studies have shown that CD4+CD25high FoxP3+ Treg cells are overrepresented in human metastatic lymph nodes with a 2-fold increased frequency
compared with both tumor-free lymph nodes and that advanced melanoma is associated with increased numbers of circulating Treg cells and Dendritic Cells (DCs) and suggested that melanoma induces immunosuppressive DCs and Treg cells in the systemic circulation of the patients . Vence et al also showed the presence of tumor antigen-specific CD4+ Treg cells in the blood of patients with metastatic melanoma.

This means the host (you) may already have the correct antigen, but the tumor and microenvironment may be suppressing the immune response by secreting suppressive cytokines like TGF- beta , IL-10, and IL -6 and or proliferating the suppressive Tregs.

Nicholaou et al most recently showed in patients with melanoma that although strong antibody responses were mounted, the generation of delayed-type hypersensitivity response was significantly impaired and patients with advanced melanoma had a significantly higher proportion of circulating CD4+ CD25+FoxP3+ Treg cells compared with those with minimal residual disease. So we now can blame the tolerance of our immune system to cancer on the T Regulatory Cells (Tregs).

It has been reported that the large number of different cell types that are claiming to be directly targeted by FoxP3+ Treg cells are CD4+, CD8+ T cell, dendritic cells, B cells, marophages, osteoblasts, mast cells, NK cells, and NKT cells.


No wonder our immune system can’t raise an attack on the Melanoma. The tumor is like a castle in the middle ages. The castle (tumor) is surrounded by a moat the (suppressive cytokines) and the walls and towers are the Tregs. If you take out walls and tower, the castle becomes vulnerable.

These Tregs when activated, upregulate the CTLA-4, CD25 (IL-2), and other receptors. So if you control the function of the Tregs, you may be able to break the tolerance of the immune system. This can be done by blocking receptors on the Treg cells


It was also noted as the tumor burden increased, so did the Tregs in the peripheral which makes it harder to eradicate tumors in the advanced stage of Melanoma.


Wieczorek et al found that Treg cell numbers are significantly increased in the peripheral blood of patients with IL-2-treated melanoma. IL-2 stimulates CXCR4 expressed on the Tregs enables the Tregs to migrate CxCL12 in the tumor microenvironment increasing the Treg accumulation.

So we need to deplete, block and limit the expansion of the Tregs. We also want to limit the concentration of Interluekin-2 at the early stage of the CD4+ T-cell expansion. This can be done in a number of ways, but why not use an antibodies that can indirectly accomplish both tasks at once. By using anti-CTLA-4 blockage we keep the activation going, causing a free for all for the cytokine IL-2 that is secreted.

CD4+ T cells regulate immune responses by producing various cytokines upon antigen stimulation. Naive CD4+ T cells have limited cytokine responses and secrete only IL-2 before they differentiate into various effector cell types CD4+ T cells regulate immune responses by producing various cytokines upon antigen stimulation. Each cell type is competing for a limited amount of IL-2 secreted by a small subset of the T helper cells. Naive T cells stimulated with antigen in the presence of IL-4 differentiate into Th2 cells secreting IL-4, IL-5, IL-10, and IL-13, whereas IL-12 induces the differentiation of naive cells into Th1 cells secreting IL-2, IFN-γ, and lymphotoxin.


FROM:
Autoimmunity: IL-21: a new player in Th17-cell differentiation
Elissa K Deenick and Stuart G Tangye
WWW.Nature.com

Ribas and Restifo et al found that if you use Anti-CTLA-4 blockade the native T-cell is pushed towards the Th17 differentiation. This causes less interleukin-2 to be produced by the CD4+ T-cells causing a shortage of IL-2 in the microenvironment for the expanding T-cells thus limiting the differentiation to Tregs. It is well known that in the presence of TGF-beta and IL-2, the Native T-cell differentiates into T Regulatory Cells.

Also the activation and differentiation of Naïve CD8+ T cells require IL-2 provided by activated CD4+ T cells at the initial priming stage within 0–2.5 hours after stimulation. Thers is
critical IL-2 signal from CD4+ cells is mediated through the IL-2R (receptor) of Naïve CD8+ cells. This activation of IL-2 signaling advances the restriction point of the cell cycle, and thereby expedites the entry of antigen-stimulated Naïve CD8+ T-cell into the S phase of the cell cycle.

The cell cycle has four stages:

1. G1 phase when the cell increases in size and gets ready to replicate its DNA.
2. S phase when the cell synthesizes or copies its chromosomes
3. G2 phase in which the cell prepares to divide
4. M phase when mitosis occurs.

If no IL-2 is available to Naïve CD8+ T-cells, they never get a chance to expand and differentiate into Cytotoxic T Lymphocytes (CTLs) Killer T-cells.
Besides promoting cell proliferation, IL-2 stimulation increases the amount of IFNγ and granzyme B produced by CD8+ T cells.

Activation and Differentiation of (CTLs) Cytotoxic T Lymphocytes

Naïve CD8+ T-cells are referred to as CTL-precursors (CTL-Ps), which are incapable of performing any function other then recognizing the class I MHC-antigen complex on the Tumor cells through the (TCR) T Cell Receptor.

For activation, the CTL-P needs at least three signals:

1. Antigen specific signal transmitted by the MHC I peptide/TCR complex for the recognition of the Antigen

2. The Costimulatory signals transmitted by the CD28 receptor and the B7 molecule of the Antigen Presenting Cells (APCs)

3. Cytokine induced signal, IL-2 interaction with the IL-2r (receptor) on the CTL-P leading to activation and differentiation of the CTL-P into effector CTL

The Cytokine IL-2 came from the(CD4+) TH1 cells which means the CTL-P is IL-2 limited and can only be activated by the secreted IL-2 if there is any to be had or by introducing IL-2 through IL-2 therapy. Now you know the reasoning behind using the IL-2 therapy as the second part of the combinatorial Therapy. If there is not enough IL-2 in the host environment, you will only get partial expansion of the CTLs. It may not be enough to eradicate large bulky tumors.

The Interluekin-2 plays another role in this Melanoma Maze. In a study by Janas et al, Il-2 increases the expressions of the perforin and granzyme A, B and C genes in the CD8+ T-cells. This increase expression causes the CD8+ T-cells to mature into Cytoxic T Lymphocytes (CTLs). The exogenous IL-2 is required for the granzyme proteins. CTLs have cytoplasmic granules that contain the proteins perforin and granzymes. A dozen or more perforin molecules insert themselves into the plasma membrane of target cells forming a pore that enables granzymes to enter the cell. Once in the tumor cell, these enzymes are able to breakup (lyse) the cell and destroy it. This is the beginning of the end for the cancer cells. The tumors begin to shrink and the rest is history.

Research suggests that the primary mode of the destruction of the tumors by CTL is by initiating death through the Fas-FasL pathway. Studies have shown that CTLs store Cytotoxic proteins in the form of granules in their cytoplasm.

These proteins belong to two categories:


1. Perforins: involved in pore formation
2. Granzymes: responsible for hydrolysis of the cellular products.

Granzymes breaks down the tumors cells just like your detergent enzymes in your laundry detergent.

Immediately following a CTL contact with the tumor cell, the Golgi sacks load with granules and granzymes which create pores to allow the granzymes to enter and destroy the tumors cells.

So now you know why Anti-CTLA-4 blockage and HD Interluekin-2 go hand and hand. Timing of the addition of IL-2 can make or break the immune response. And without suppressing the Tregs, your chances to mount an immune response may be slim at best. Your Immune System is a well Orchestrated system of events; we just need the Knowledge on how to harvest its potential on eradicating cancer.


The beginning of knowledge is the discovery of something we do not understand.
~Frank Hebert~
A critically acclaimed and commercially successful American science fiction author


Take Care,

Jimmy B
Photobucket

Tuesday, March 9, 2010

Challenges and Opportunities Ahead..Melanoma Therapy ..Jim Breitfeller

"A dynamic picture is emerging in which the immune system is far from quiescent in cancer, and tumor cells elaborate a host of countermeasures to evade immune destruction. In essence, these are two systems which co-evolve over time. Clinical outcome is ultimately a balance between the proliferation of tumor cells and the immune response which attempts to control these cells. Various treatments may perturb these two systems in different ways - in good clinical outcomes, the immune response ultimately dominates, while in poor outcomes, tumor cells dominate.

It is becoming clear that the challenge in tumor immunotherapy lies not only in lack of tumor recognition, but also ineffectivity of the immune response that develops. While efforts to elicit tumor-specific T cells directly in patients via vaccination may overcome potential mechanisms of immune evasion by tumors cells, current immunotherapeutic strategies do not address their potential immunomodulatory mechanisms.

Understanding the molecular mechanisms which underlie T cell dysfunction in cancer will be important to devise novel adjunct strategies to enhance or modulate T cell responses after tumor-specific T cells have been elicited. It will likely take a multi-faceted approach acting at several steps along the T cell activation and effector activity pathway to finally achieve success in cancer immunotherapy."


The Laboratory of Peter P. Lee, MD at Stanford University

This multi-faceted approach acting at several steps along the T cell activation and effector activity pathway is what I call Combinatorial Therapy.

We first start at obtaining the Antigen to be presented on the Antigen Presenting Cell. Then once we think we got it, we need to proceed to the Activation step. Ipilimumab (Anti-CTLA-4 Blockade) helps to keep the activation in the on position. It also has a dual role, in keep the Treg's surpressive function out of play in the Tumor 's microenvirioment.
Interleukin -2 is the final step to complete response. It is the growth factor for the CTL's, which help maintain functionality and survival of the Cytotoxic T Lymphocytes (CTL's).


Take Care,

Jimmy B
Photobucket

Friday, June 12, 2009

Peptide Vaccine Significantly Improves Response in Metastatic Melanoma, but also Rasies questions.Melanoma..Jim Breitfeller

Peptide Vaccine Significantly Improves Response in Metastatic Melanoma, but also Rasies questions.

The current study raises several questions, Dr. Ribas said, including the following:
Question- How does high-dose IL-2 induce tumor regression? "With over 20 years of study, we still don't have an answer."

Answer_I have a theory: The NaiveCD4 + the helper T cell, when activated, the Helper T –cell secretes mostly IL-2 which promotes growth and proliferation, and activation of T-cells, helper T cells and Natural Killer Cells. Once the helper cells mulitply, they start secreting other cytokines base on their costimulatory signals., concentration of antigen, and exposure to their microenviroment. This attracts more immune cells and the assault on the foreign invader begins. The HD IL-2 helps activates the CD4-T cell.Cell to to cell comunication.

At the Lymp Node drainage area, the lymphocytes (CD4+ and CD8+) with their T-cell receptors (TCRs) are able to scan the Dendtric cells (DC’s) for antigen-MHC molecules. (ag-MHC) major histocompatability complex (class I or II). Based on the two signal model, a second signal from CD28 molecule is needed to activate the T-cells (T-lymphocytes). If communcation breaksdown, and the TCR signal only happens, it can lead to tolerance by means of fuctional paralysis of the (APCs) Antigen presenting cells (Anergy) or by the induction of clonal deletion (apoptosis).

Anergic cells can act as regulatory T cells by competing at the sites of antigen presentation and adsorbing out stimulatory cytokines such as IL-2. This can halt the activation of the T- lymphocytes and no immune response is initiated. But after activation of the CD4+ T cells and growth of the T- cells, they cross-prime the CD8+ T cells and in the presence of HD IL-2 mature into (CTL) Cytotoxic T lymphocytes. Cross-priming is another name for cross-presentation. The role of the CD8+ T cells is to monitor all the cells of the body, ready to destroy any that express foreign antigen fragments in their class I molecules.

CTLs have cytoplasmic granules that contain the proteins perforin and granzymes. When the CTL binds to its target, the contents of the granules are discharged. A dozen or more perforin molecules insert themselves into the plasma membrane of target cells forming a pore that enables granzymes to enter the cell. Granzymes are serine proteases. The serine proteases are a family of enzymes that cut certain bonds in other proteins. It is similar to what is in your laundry detergent. They are known as detergent enzymes. They break the bond between the dirt and the fabric. By breaking up these proteins, they start destroying the intracellular workings of the tumor cells.

Question- How do gp100 peptides improve outcomes of high-dose IL-2?


Answer-My guess, They attach to the Antigenic protein and form some sort of a complex and when the complex is processed by the Antigen Presenting Cell you now have more antigenic fragments then you would other wise, which means activating more T-cells improving the microenvironment.

Photobucket

Photobucket


The answers are base on my research and intuition.


Take Care,

Jimmy B
Photobucket

Greetings to One and All

This Blog is dedicated My Brother Kenny B. who passed away in the late 1970's with Cancer before the Internet.

It was he, who showed me How to live and give back. He was wise beyond his years.


Kenny B


Jimmy and Dee

Carepage: Jimmybreitfeller
Jimmy Breitfeller


My Profile as of 2009

My photo
Last July (2005)I was riding my bicycle to work at the Eastman Kodak Research Labs about 3 miles from home. I was wearing a knapsack to carry my things to and from the labs. I started noticing an ache on my back. So I decide to go to the dermatologist. To make the long story short, it was cancer. I knew from my research that I would be needing adjuvant therapy. So I started communicating with Sloan Kettering, University of Pittsburgh Cancer Center, and a couple of others including the Wilmot Cancer Center at Strong. I realized that by telling my story, I might help someone else out there in a similar situation. So to all who are linked by diagnosis or by relation to someone with melanoma, I wish you well. Stay positive, read as much as you can (information helps to eliminate the fear associated with the unknown), and live for today, as no one can predict what tomorrow may bring. Jimmy B. posted 12/15/08

Disclaimer

The information contained within this Blog is not meant to replace the examination or advice of your Oncologist or Medical Team. The educational material that is covered here or Linked to, does not cover every detail of each disorder discussed.

Only your physician/Oncologist can make medical decisions and treatment plans that are appropriate for you. But, An Educated Consumer is a Smart consumer.

As Dr. Casey Culberson Said:

"The BEST melanoma patient is an ACTIVE PARTICIPANT in his or her treatment
(not a PASSIVE RECIPIENT)"

Melanoma and the “Magic Bullet” (Monoclonal Antibodies)

Just to let you know I posted the first draft of the Melanoma and the “Magic Bullet” (Monoclonal Antibodies). on Melanoma Missionary In the Shared File Section. you can download it for 19.95 (Only kidding) it is Free for the taking.


It is 33 pages long and may help you in your quest for the Yellow Brick Broad. Just to let you know it is only the first draft. Revisions are sure to come. I wanted to get it to the people that need it the most, the Melanoma Patients.

Preview:

So, where does Interluekin-2 (IL-2) come into play? According to Byung-Scok et al and recent reports, IL-2 is not needed for developmental CD4+ CD25+ Treg cells in the thymus but does play an important role in the maintenance and function in the peripheral.18 Peripheral is defines as secondary system outside the bone marrow and thymus. It entails the site of antigen, immune system interaction. IL-2 is required for the peripheral generation of Tregs based Abbas’s and colleagues research.19

IL-2 prevents the spontaneous apoptosis of the CD4+ CD25+ Treg cells. It has been reported that patients with multiple advance-stage tumors have elevated levels of Tregs within the tumor microenviroment.20 Interluekin-2 is the survival factor for CD4+ CD25+ Treg cells.21 If the addition of IL-2 is on or before the maximum propagation of the CD4+ T cells, the Tregs population can increase 5-fold in a 96 hour period based on certain growth mediums.

By controlling the addition of the endogenous IL-2, one has a knob to turn and can lead to the control of the expansion of the Tregs. When you combined this control with the anti-CTLA-4 blockage, you can shift the balance of the immune response.

Now here is the catch. The maintenance and function of the CD8+ T-cells require CD4+ cells which secrete IL-2. So we don’t want to deplete the CD4+ cells, we want to control the expansion of the Tregs which are a subset of the CD4+ cells. It has been postulated by some researchers that the Anti-CTLA-4 blockage also suppresses the Treg function in a different mechanism. By using IL-2 as the rate limiting factor, we can suppress the CD4+ CD25+ Treg cell expansion by controlling the concentration and timing of the Inerluekin-2 at the tumor microenvironment.


The Interluekin-2 plays another role in this Melanoma Maze. In a study by Janas et al, Il-2 increases the expressions of the perforin and granzyme A, B and C genes in the CD8+ T-cells. This increase expression causes the CD8+ T-cells to mature into Cytoxic T Lymphocytes (CTLs). The exogenous IL-2 is required for the granzyme proteins. As stated previously, CTLs have cytoplasmic granules that contain the proteins perforin and granzymes. A dozen or more perforin molecules insert themselves into the plasma membrane of target cells forming a pore that enables granzymes to enter the cell. Once in the tumor cell, these enzymes are able to breakup (lyse) the cell and destroy it. This is the beginning of the end for the cancer cells. The tumors begin to shrink and the rest is history,

“

On the other hand, prolong therapy with Il-2 can result in causing apoptotic death of the tumor- specific CD8+ T-cells.23

Clearly in a clinical setting, timing, dose, and exposure to these drugs play a major roll in the immunotherapy, and can have dramatic effects on the outcome.

All it takes is that one magic bullet to start the immune reaction..

https://app.box.com/shared/kjgr6dkztj

Melanoma And The Magic Bullet (Monoclonal Antibodies)

Public Service Announcement

A call for Melanoma Patients by Dr. Steven A Rosenberg

"We continue to see a high rate of clinical responses in our cell transfer immunotherapy treatments for patients with metastatic melanoma", Dr. Rosenberg said.

"We are actively seeking patients for these trials and any note of that on a patient-directed web site would be appreciated."

If you would like to apply for his trials, here is the website and information.

Dr. Rosenberg's information


Dr. Rosenberg's Clinical Trials


For the Warriors


The Melanoma Research Alliance has partnered with Bruce Springsteen, the E Street Band, and the Federici family to alleviate suffering and death from melanoma. Please view Bruce Springsteen’s public service announcement inspired by Danny Federici. Danny was the E Street Band’s organist and keyboard player. He died on April 17, 2008 at Memorial Sloan-Kettering Cancer Center in New York City after a three year battle with melanoma.


http://www.melanomaresearchalliance.org/news/PSA/

Source Fastcures blog


Join the Relay for Life!!!

Photobucket

Dear Family and Friends,

I’ve decided to take a stand and fight back against cancer by participating in the American Cancer Society Relay For Life® event right here in my community! Please support me in this important cause by making a secure, tax-deductible donation online using the link below.

To donate on line now, click here to visit my personal page.
Jimmy B AKA Melanoma_Missionary

Relay For Life® is a life-changing event that brings together more than 3.5 million people worldwide to:

CELEBRATE the lives of those who have battled cancer. The strength of survivors inspires others to continue to fight.

REMEMBER loved ones lost to the disease. At Relay, people who have walked alongside people battling cancer can grieve and find healing.

FIGHT BACK. We Relay because we have been touched by cancer and desperately want to put an end to the disease.

Whatever you can give will help - it all adds up! I greatly appreciate your support and will keep you posted on my progress.

Keep the Fire Burning!!!

Photobucket

Sincerely,

Jimmy Breitfeller
Turn off Music before you "Click to Play"
Signs of Melanoma Carcinoma Skin Cancer

How Skin Cancer Develops by "About.com : Dermatology"

Call for Patients with Unresectable Liver Metastases Due to Melanoma


Delcath Systems Granted Orphan-Drug Designations for Cutaneous and Ocular Melanoma


Delcath is actively enrolling patients in a Phase III clinical trial testing its proprietary drug delivery system, known as Percutaneous Hepatic Perfusion (“PHP”), with melphalan for the treatment of ocular and cutaneous melanoma metastatic to the liver.

This NCI-led trial is enrolling patients at leading cancer centers throughout the United States. Commenting on these orphan-drug designations, Richard L. Taney, President and CEO of Delcath, stated, “These favorable designations are important steps in our efforts to secure Delcath’s commercial position upon conclusion of our pivotal Phase III trial for metastatic melanoma. We remain steadfast in our commitment to become the leader in the regional treatment of liver cancers and we continue to enroll patients in this study, and advance our technology and the promise that it offers to patients with these deadly forms of melanoma and other cancers of the liver, all with limited treatment options.”

Orphan drug designation, when granted by the FDA’s Office of Orphan Products Development, allows for up to seven years of market exclusivity upon FDA approval, as well as clinical study incentives, study design assistance, waivers of certain FDA user fees, and potential tax credits.


Current Trial Centers


Phase I Study of Hepatic Arterial Melphalan Infusion and Hepatic Venous Hemofiltration Using
Percutaneously Placed Catheters in Patients With Unresectable Hepatic Malignancies


James F. Pingpank, Jr., MD, FACS
Associate Professor of Surgery
Division of Surgical Oncology
Suite 406, UPMC Cancer Pavillion
5150 Centre Avenue
Pittsburgh, PA 15232
412-692-2852 (Office)
412-692-2520 (Fax)
PingpankJF@UPMC.edu


Blog Archive

Call For Melanoma Patients!!!!

Call For Melanoma Patients!!!!

Dr. Rosenberg Has a New Clinical Trial.

Our latest treatment has a 72% objective response rate with 36% complete responses.

We are currently recruiting patients for our latest trial.

Is there some way to post this “Call for Patients” on the web site?

Steve Rosenberg

Dr. Rosenberg's Clinical Trials


(For a copy of the research paper.. see My Shared files)

The news headlines shown above for Melanoma / Skin Cancer are provided courtesy of Medical News Today.